Home insemination in the UK: timing, safety, and legal basics
Home insemination places semen in the vagina with a needle-free syringe to try to conceive without intercourse. This guide explains timing around ovulation, safe handling of fresh donor sperm, hygiene, realistic success rates, costs, and key UK legal questions when a known donor is involved.


What home insemination means
Home insemination usually means placing semen into the vagina, close to the cervix, so sperm can travel on their own through the cervix and uterus. It is an at-home attempt to create the same starting point that intercourse would create, but without sex.
Home insemination, at-home insemination, and self-insemination usually describe the same basic process. Phrases such as the cup-and-syringe method simply describe how the semen is collected and transferred.
- Closest medical description: intravaginal insemination (IVI). ICI is different because semen is placed at or in the cervix.
- Core goal: sperm present during the fertile window, with gentle handling and clean supplies.
- Core limitation: no clinical diagnosis, no lab processing, and no placement into the uterus.
Why DIY IUI and sperm washing do not belong at home
IUI, or intrauterine insemination, is a clinic procedure that places prepared sperm into the uterus using medical equipment and lab processing. It is not a home-insemination technique.
That difference matters. IUI changes where sperm are placed and how the sample is prepared, and it is done under clinical protocols. If your goal is IUI, it is safer to treat it as a clinic decision rather than an at-home project.
Sperm washing is also a laboratory process used for specific clinic procedures and safety protocols. It cannot be reliably replicated at home.
If you want a clear overview of how trying to conceive works and how to improve your chances in everyday life, the NHS guide is a solid starting point. NHS: Trying to get pregnant
The biology that actually drives your odds
Home insemination succeeds when sperm are present in the reproductive tract during the fertile window. The egg is fertilisable for a relatively short time after ovulation, while sperm can sometimes survive for several days in supportive cervical mucus.
That is why timing usually matters more than small technique tweaks. A practical way to reduce guesswork is to track cycles consistently and use an approach that helps you identify your most fertile days. NHS: Fertile window basics
- Most avoidable misses are timing-related, not tool-related.
- Consistency across cycles helps you learn what is working and what is not.
- If cycles are irregular, confirming ovulation can matter more than repeating attempts.
Who home insemination may suit — and when it may not
Home insemination is often used when pregnancy is being attempted without intercourse, including many LGBTQ+ families, solo parents by choice, and people who want a lower-intervention starting point before clinic treatment.
Often a reasonable fit
- Regular cycles with a trackable fertile window
- No known tubal disease and no major red flags from prior medical history
- Clear plan for screening and consent, especially with a known donor
Often worth a clinic conversation sooner
- Very irregular cycles or repeated unclear ovulation tracking
- History suggesting tubal disease, severe endometriosis, or significant pelvic infections
- Known severe sperm factor or repeated failed attempts with well-timed cycles
- Recurrent pregnancy loss
Realistic success rates
There is no single success rate that applies to everyone. Research specifically measuring at-home insemination is limited because methods, starting points, and documentation vary widely.
What you can do is keep expectations grounded and focus on the variables that reliably matter in conception attempts: age, ovulation timing, semen quality, and whether there are underlying fertility factors.
- Timing within the fertile window is the biggest controllable factor.
- More complexity does not automatically mean better odds.
- A reassessment plan prevents months of repeated uncertainty.
A clean, practical process overview
A consistent routine helps keep the handling gentle and the timing clear. The overview below is general education, not personalised medical instruction.
What to prioritise
- Clean setup and single-use supplies
- Minimal delay between collection and insemination
- Stable temperature and gentle handling
- No force, no pain, and no attempts to pass through the cervix
Common structure
- Plan timing around the fertile window.
- Collect semen into a clean container.
- Allow a short time at room temperature if needed for normal liquefaction.
- Transfer gently into a needle-free syringe or a soft catheter designed for vaginal placement.
- Place the semen gently into the vagina, then return to normal activity when comfortable.

A ready-made kit is optional. It can make preparation more convenient, but it does not improve fertility by itself. Compare whether a set contains a few suitable single-use items or mainly expensive extras and big success claims. Our guide to home insemination kits explains useful contents and common marketing traps.
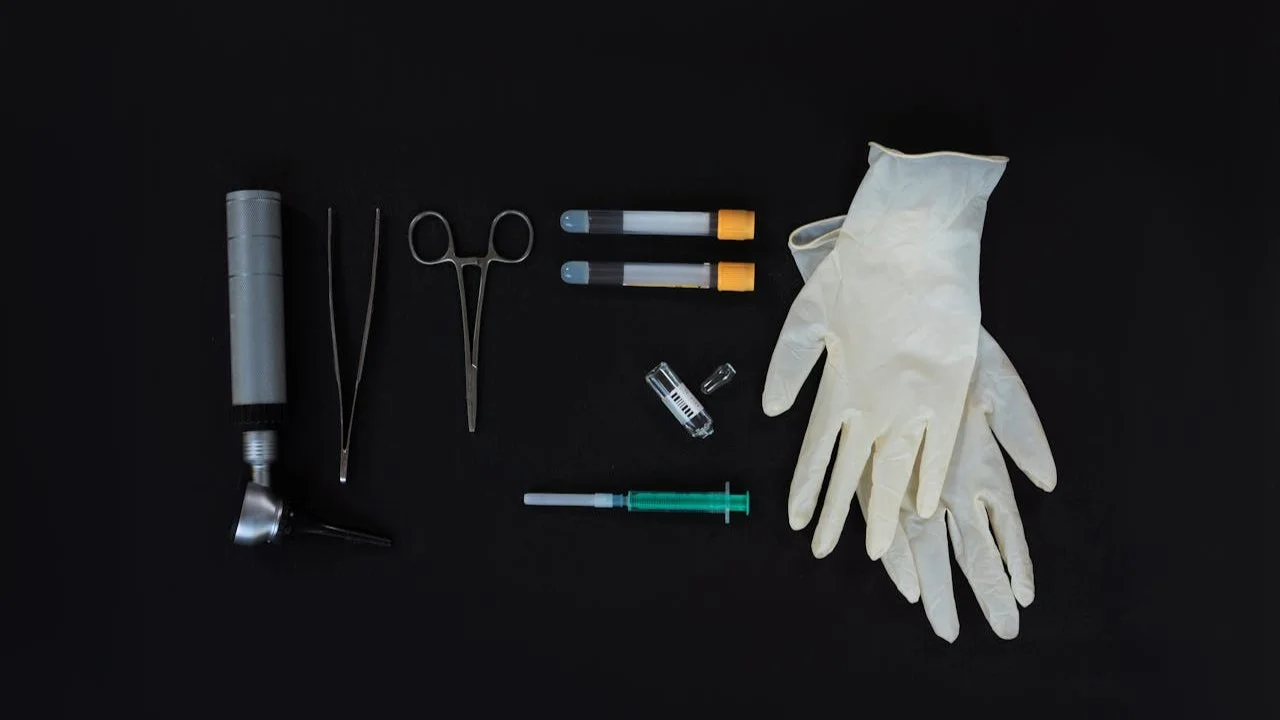
For most attempts, the practical minimum is a sterile or suitably clean wide-mouth specimen pot, an individually wrapped needle-free syringe with a controllable plunger, and a clean surface. Disposable gloves are optional; ovulation tests can help with timing.
Needles, rigid cervical catheters, reusable applicators, fragrances, oils and so-called sperm activators are not basic supplies. Do not try to wash or select sperm at home. Use a fresh sample promptly without deliberately heating or chilling it; the guide How long sperm survive explains the differences between survival in the body, in a pot and after drying.
Timing in real life
Ovulation predictor kits detect an LH surge. Ovulation often follows, but the gap can vary by person and by cycle. A practical approach is to cover the fertile window instead of betting everything on one exact hour.
What many people do
- Use ovulation tests consistently to learn your pattern.
- Plan an attempt close to a clear positive test result.
- Consider one additional attempt within the next day if timing uncertainty is high and logistics allow.
When timing becomes the bottleneck
If ovulation tests are consistently confusing, cycles vary widely, or you rarely see a clear surge, confirming ovulation with a clinician can be more effective than repeating guesses.
Fresh donor sperm: how long it lasts in a cup and what matters
Fresh sperm does not have one fixed survival time in a sample pot. Motility depends on time, temperature, drying, and exposure to harsh conditions.
Practical takeaways
- Plan for minimal delay between collection and insemination.
- Keep the sample at stable room temperature.
- Avoid heating, chilling, or home freezing experiments.
- Avoid drying on surfaces and avoid unnecessary air exposure.
- Handle gently. Stirring or shaking is rarely helpful.
Can sperm survive in a syringe?
This question is common because people worry the syringe itself will harm sperm. In practice, the bigger risks are long delays, overheating, and drying. Short contact with a clean, appropriate syringe is usually less important than the overall handling conditions.
- Transfer gently and avoid repeatedly drawing up and expelling.
- Minimise time between transfer and insemination.
- If pain or irritation occurs, prioritise comfort and safety and simplify the approach.
How much sperm is needed?
People often want a specific volume number, but volume alone is not the deciding factor. What matters more is how many motile sperm are present and whether timing matches the fertile window.
If you are using frozen donor sperm, vial type and motile count after thaw can matter. Match the product and handling instructions to the method you are actually using rather than assuming every vial is equivalent.
What tends to improve results?
Most helpful improvements are boring and repeatable. They are also the same improvements that help conception attempts in general.
- Track ovulation consistently so attempts cover the fertile window.
- Reduce avoidable delays with fresh samples.
- Avoid temperature extremes and drying.
- Keep the routine consistent across cycles.
- Set a reassessment point and follow it.
Common pitfalls
Many people assume technique is the missing piece, when timing is the real issue. Another common pattern is making the process more complicated each cycle, which increases stress and makes it harder to learn what helps.
- Inseminating outside the fertile window
- Long delays after collection
- Exposure to heat, cold, or direct sunlight
- Reusing supplies that are difficult to clean reliably
- Trying to turn home insemination into an at-home version of IUI
- Part of the sample was spilt
- Use only the portion that stayed clean in the pot. Do not return semen from skin, fabric or a work surface, scrape it up or add water. A partly lost sample does not automatically mean the cycle has failed.
- The amount looks small or the sample is still thick
- Visible volume alone shows neither sperm count nor motility. Do not dilute the sample with water, saline or lubricant. Fresh semen is often thick at first and commonly liquefies at room temperature in about 15 to 30 minutes, as described in the WHO laboratory manual. Do not heat it, shake it hard or mix in other liquids. If the amount is repeatedly very low, the sample remains unusually thick or several well-timed attempts fail, a semen analysis can assess the starting point more reliably.
- There are small air bubbles in the syringe
- Draw up slowly and avoid foam. A few small bubbles do not require repeated transfers between pot and syringe or discarding the sample. The syringe must be needle-free, used only in the vagina and emptied slowly.
- Semen flows back out
- Some leakage is expected and does not prove failure because the vagina is not sealed. A few quiet minutes lying down are optional; prolonged lying, raised legs or a headstand are not reliable ways to improve the odds.
- Insertion hurts
- Stop, do not push deeper and do not use an improvised catheter. End the attempt if there is pain, bleeding or clear resistance. Persistent pain, fever, heavy bleeding or unusual or foul-smelling discharge warrants medical review.
- The first part of the ejaculation was missed or contaminated
- Do not return semen from skin, fabric or a work surface to the pot. Note if the first fraction was not collected because it often contains a high concentration of sperm. The remaining clean sample is not automatically useless, but it is harder to assess.
Hygiene, STI screening, and safety
At-home insemination is not sterile surgery, but hygiene is not optional. Use single-use supplies, wash hands, and set up a clean surface. Avoid reusing items that are hard to clean reliably.
Known donor basics
- Talk openly about recent STI testing and agree on a retesting schedule if attempts continue.
- Discuss boundaries and expectations before the first attempt, not after a pregnancy test.
- Consent should be clear and ongoing for everyone involved.
Do not rely on verbal reassurance alone. Review dated health and STI results, discuss medicines and relevant family history, and agree what should be repeated if attempts continue. Our guides to donor health information and carrier screening before sperm donation help structure that review.
Before the first attempt, also discuss the donor's intended role, future contact, privacy, and how the child's origins will be handled. Record consent and the handover clearly. The questions to ask a sperm donor and the guide to safe semen transport cover these separate decisions in more depth.

Knowing and trusting a donor—or knowing that he has fathered a child—does not establish current infection status, semen quality or inherited risk. A negative test lowers risk but can miss a very recent infection. The ASRM guidance on gamete donation therefore combines medical and family history, current infection testing, genetic risk assessment and clear documentation.
- Verify health information, not just verbal reassurance
- Keep dated, identifiable laboratory results and ask a qualified clinician which tests and repeat intervals fit the situation. Discuss medicines, relevant family history and any new exposure between testing and donation.
- Agree on role, contact and boundaries before the first attempt
- Sample handover does not decide a donor's future social role. Discuss contact, privacy, consent and how the child's origins will be handled before ovulation timing creates pressure.
- Make the handover traceable
- Record the date and time of collection, whose tested sample it is, whether the complete sample was collected without contamination, and any transport interval. Keep the route short and direct when transport is necessary.
Home insemination does not make a known-donor sample sterile or medically cleared. Postpone the attempt and seek qualified advice if results are unclear, a new risk occurred after testing, or anyone is being pressured. If lubricant is needed, use a small amount of a product specifically labelled sperm-friendly; saliva, oils, spermicides and arbitrary lubricants are poor substitutes.
If you need lubrication, be cautious. Many common vaginal lubricants can reduce sperm movement and some fertility clinics advise avoiding them when trying to conceive. PMC: Vaginal lubricants and sperm toxicity
Seek medical care promptly for fever, severe pelvic pain, heavy bleeding, fainting, or foul-smelling discharge.
Costs and practical planning in the UK
At-home costs usually come from ovulation tests, pregnancy tests, single-use supplies, and any screening you add. Costs can rise significantly with frozen donor sperm because shipping and storage conditions are specialised and time-sensitive.
If you plan to use donor sperm through a clinic, factor in appointment fees, counselling requirements, and the clinic’s storage and scheduling timelines. If you are hoping for NHS-funded fertility care, eligibility and access can vary by where you live and by local commissioning policies.
A planning mindset that prevents burnout
- Decide how many well-timed cycles you will try before reassessing.
- Track timing, sample handling time, and ovulation test results.
- Define what would trigger a GP appointment or fertility referral so you do not keep guessing.
Legal and regulatory context in the UK
Legal parenthood and donor arrangements in the UK are closely tied to where and how donor sperm is used. Using donor sperm through an HFEA-licensed fertility clinic provides formal safeguards around screening, records, and legal parenthood.
If you are considering home insemination with donor sperm, the HFEA highlights an important risk: in some situations the donor may be treated as the legal parent, with rights and responsibilities, particularly when you are not married or in a civil partnership. HFEA: Home insemination with donor sperm
For people using donor sperm in treatment, legal parenthood can also depend on consent forms and the accuracy of clinic documentation, especially for couples who are not married or in a civil partnership. HFEA: Becoming the legal parents of your child
Government guidance for donors also notes that donating outside licensed treatment can affect legal status. GOV.UK: Legal rights for egg and sperm donors
This is not legal advice. If a known donor is involved, or if you are planning co-parenting, it is often sensible to speak with a solicitor who understands family law and assisted reproduction in your part of the UK. International rules may differ substantially, so do not assume UK norms transfer to other countries.
When medical advice is a good next step
You do not need to wait until you want IVF to ask for help. A GP can review cycle patterns, check common causes, and refer you to a fertility service when that would save time.
The NHS advises seeing a GP if you have not conceived after a year of trying, and sooner if you are aged 36 or over or have reasons to be concerned about fertility. NHS: Infertility diagnosis and when to get help
NICE referral guidance also recognises artificial insemination cycles as a benchmark for seeking specialist input when pregnancy has not happened. NICE: Referral after 1 year or 6 cycles of insemination
- Consider a GP appointment after around 12 months of well-timed attempts, or sooner if aged 36 or over.
- Consider earlier review with very irregular cycles, significant pelvic pain, known tubal issues, or recurrent pregnancy loss.
- If you are doing insemination cycles, consider reassessing after several well-timed cycles rather than continuing indefinitely.
Conclusion
Home insemination can be a reasonable path in the UK when it is well-timed, handled gently, and approached with realistic expectations. Most of the advantage comes from covering the fertile window and avoiding avoidable handling and hygiene mistakes.
Read more
More on insemination kits, ovulation timing, donor health evidence, and safe semen transport.