Semen: composition, volume and sperm quality
Semen contains much more than sperm cells: most of it is fluid that nourishes and transports them. This article explains how semen and sperm are produced, their role in fertilisation, and what volume, colour, and consistency can tell you. It also covers how sperm quality is assessed and which changes are worth discussing with a doctor.


What is semen, and what is it made of?
Semen is the fluid released during ejaculation. It is also called ejaculate. Sperm are the reproductive cells it contains; the fluid portion without these cells is called seminal plasma. This distinction explains why a large volume of semen does not automatically mean a high sperm count.
Seminal plasma is mostly water, but it also contains proteins, enzymes, sugars, and minerals. It nourishes sperm cells and provides the fluid in which they leave the body during ejaculation. Several organs contribute:
- Testicles and epididymides
- Sperm cells are produced and continue maturing here. Their contribution to the total fluid volume is relatively small.
- Seminal vesicles
- These supply a large proportion of the seminal fluid, including fructose as an energy source for sperm.
- Prostate
- Its secretions contain enzymes, among other substances, that help semen liquefy after ejaculation.
- Cowper's glands and other small glands
- These add mucus-like secretions that lubricate the urethra. Pre-ejaculate is released before ejaculation and is distinct from semen itself.
These components mix during ejaculation as they travel through the reproductive ducts. Despite their name, the seminal vesicles do not store fully developed sperm. The glands' contributions are described in the medical overview in Endotext.
How is a sperm cell structured?
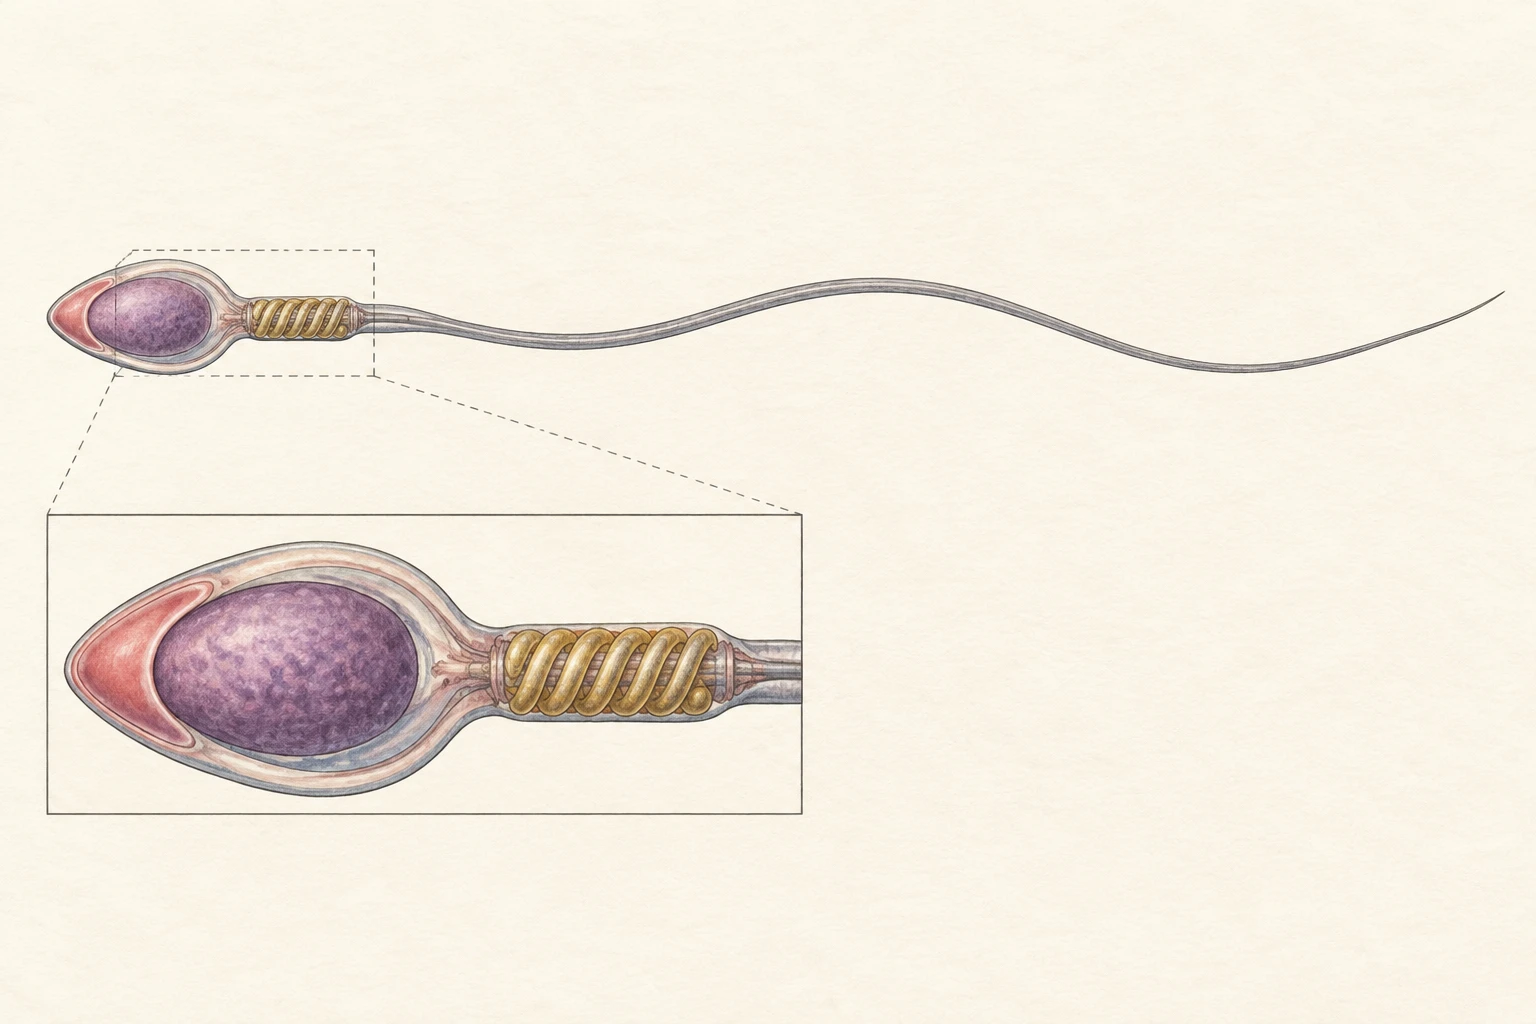
A sperm cell is specialised for its task: carrying genetic material to the egg. It has three distinct parts:
- Head: This contains the nucleus and its genetic material.
- Midpiece: This contains many mitochondria, which help supply the cell with energy.
- Tail: This long flagellum enables the cell to move.
Sperm are produced through a special type of cell division called meiosis. As a result, they normally contain 23 chromosomes, or one set. At fertilisation, the egg contributes another 23 chromosomes. MedlinePlus explains cell division and how this works.
Suitable shape and movement matter. But whether a sperm cell can fertilise an egg also depends on processes that a routine look through a microscope cannot fully assess.
How are sperm produced, and how long does it take?
The testicles begin continuously producing sperm cells at puberty. Production and maturation take about three months in total. Because new cells are always maturing, the body does not have to start over after every ejaculation.
Sperm continue maturing in the epididymis, where they are also stored. During ejaculation, they travel through the vas deferens to the urethra. The body breaks down sperm cells that are not ejaculated. You do not need to ejaculate to prevent a harmful buildup. familienplanung.de explains sperm production and this process.
This long maturation period also matters medically: after a fever or another significant strain on the body, changes may not appear in a semen sample immediately. Likewise, the benefits of treatment or lifestyle changes cannot be judged after just a few days.
What happens to sperm after ejaculation?
After ejaculation into the vagina, sperm can travel through the cervix and uterus toward the fallopian tubes. Fertilization usually takes place in a fallopian tube if an egg is present.
Along the way, sperm undergo changes that enable them to fertilise an egg. This process is called capacitation. It illustrates why fertility involves more than whether sperm are present and moving.
Under favourable conditions, sperm can survive in the female reproductive tract for up to five days. This does not apply to dried semen on skin or clothing. For a detailed explanation of different situations, see How long do sperm survive?
It is normal for some semen to leak out after sex, and this does not mean all the sperm have been lost. According to the ASRM committee opinion on natural fertility, lying down afterward or using particular sex positions has not been shown to improve the chances of pregnancy.
How much semen is normal?
An ejaculation usually produces a few millilitres. The amount varies with factors such as time since the last ejaculation and whether the whole sample was collected. Several ejaculations close together may produce smaller volumes. The amount you can see is not a measure of sexual performance or fertility.
A laboratory assesses volume under standardised conditions. The EAU guideline gives the WHO lower reference limit as 1.4 millilitres. This value describes the lower end of the distribution among men whose partners became pregnant within a year. It is not a dividing line between fertile and infertile, or a target for every everyday ejaculation.
If you repeatedly release unusually little fluid or none at all despite having an orgasm, a medical assessment is worthwhile. Sample collection, medications, ejaculation backward into the bladder, or an obstruction can be among the explanations. The Cleveland Clinic overview of semen describes possible causes. Volume alone cannot tell you which one applies.
Colour and consistency: what is normal, and what can changes mean?
Semen is typically whitish to greyish-white. Immediately after ejaculation, it can be thick, gel-like, or slightly uneven. It usually becomes more liquid afterward, often within about 15 to 30 minutes. Looking at it immediately after ejaculation can therefore give a different impression than looking at it later.
A single variation can be difficult to interpret. Notice whether the change is new, happens repeatedly, or comes with symptoms.
- More watery than usual
- This can be normal variation, for example after frequent ejaculation. It does not establish a low sperm count. If the change persists or you are having difficulty conceiving, an assessment is worthwhile.
- Slightly yellow
- A yellowish tint does not automatically mean an infection. It can have several causes, often harmless. A clear new change in colour with burning, discharge, or pain is worth discussing with a doctor. The Cleveland Clinic information on yellow semen explains more.
- Small clumps
- These can be part of the initial gel formation. A laboratory assesses whether liquefaction or viscosity is abnormal. Visible clumps alone do not prove inflammation.
- Pink, red, or brown
- This can indicate fresh or older blood. The cause is often not dangerous, but you should still have blood in semen checked by a doctor.
Smell, blacklight, and other everyday observations are covered in Unusual questions about semen. Taste, pineapple, and swallowing semen are covered separately in the article on the taste of semen.
Symptoms that deserve medical attention
Appearance cannot reliably tell you whether a sexually transmitted infection is present. Many infections cause no visible changes or symptoms. Appropriate tests matter after a possible exposure; a good semen analysis does not confirm that you are free of infection. The NHS information on sexually transmitted infections explains symptoms and testing options.
Pain or other new symptoms should be assessed regardless of what your semen looks like. These include:
- Burning when you urinate, discharge, or sores in the genital area.
- Pain during ejaculation or persistent pelvic discomfort.
- Blood in semen or urine.
- A lump, swelling, or new pain in a testicle.
- Fever along with genital symptoms or symptoms when urinating.
The NHS information on blood in semen recommends getting checked even though the cause is often harmless. Seek immediate medical attention for sudden, severe testicular pain. One possible cause is testicular torsion, in which the spermatic cord twists and threatens the testicle's blood supply. The NHS information on testicle pain also highlights this risk.
What does sperm quality mean, and what does a semen analysis measure?
Sperm quality refers to several characteristics, including the number of sperm cells, how they move, and their shape. A semen analysis measures these and other features of a sample using standardised methods. The WHO laboratory manual for examining human semen describes these methods.
Here are the main distinctions:
- Volume
- How much seminal fluid was collected. This is different from sperm count.
- Concentration and total count
- Concentration is the number per millilitre; total count refers to the entire ejaculate.
- Motility
- This includes assessing the proportion of sperm moving forward. A sperm cell that moves does not necessarily make good forward progress.
- Morphology
- This means sperm cell shape, assessed under a microscope according to defined criteria.
- Vitality
- This is the proportion of living sperm. A sperm cell that is not moving is not necessarily dead.
A simple calculation shows the difference between volume and concentration: a 3-millilitre sample containing 20 million sperm per millilitre has 60 million sperm in total. That still tells you nothing about motility or shape. This is an illustration, not a model test result.
Even an apparently normal ejaculation can contain no detectable sperm. This is called azoospermia and cannot be identified by appearance.
Reference values are guides, not a rigid boundary between fertile and infertile. Results within the reference ranges do not guarantee pregnancy, and one abnormal value does not automatically rule out natural conception. The EAU guideline on male infertility emphasises that semen analysis alone cannot make this distinction.
Depending on the question being investigated, liquefaction, viscosity, and pH may also be assessed. Home tests often measure only selected characteristics, such as concentration or motility. They provide less information than a complete semen analysis and do not replace medical assessment when you have symptoms or difficulty conceiving. MedlinePlus explains semen analysis and the distinction.
DNA fragmentation: what the standard test does not measure
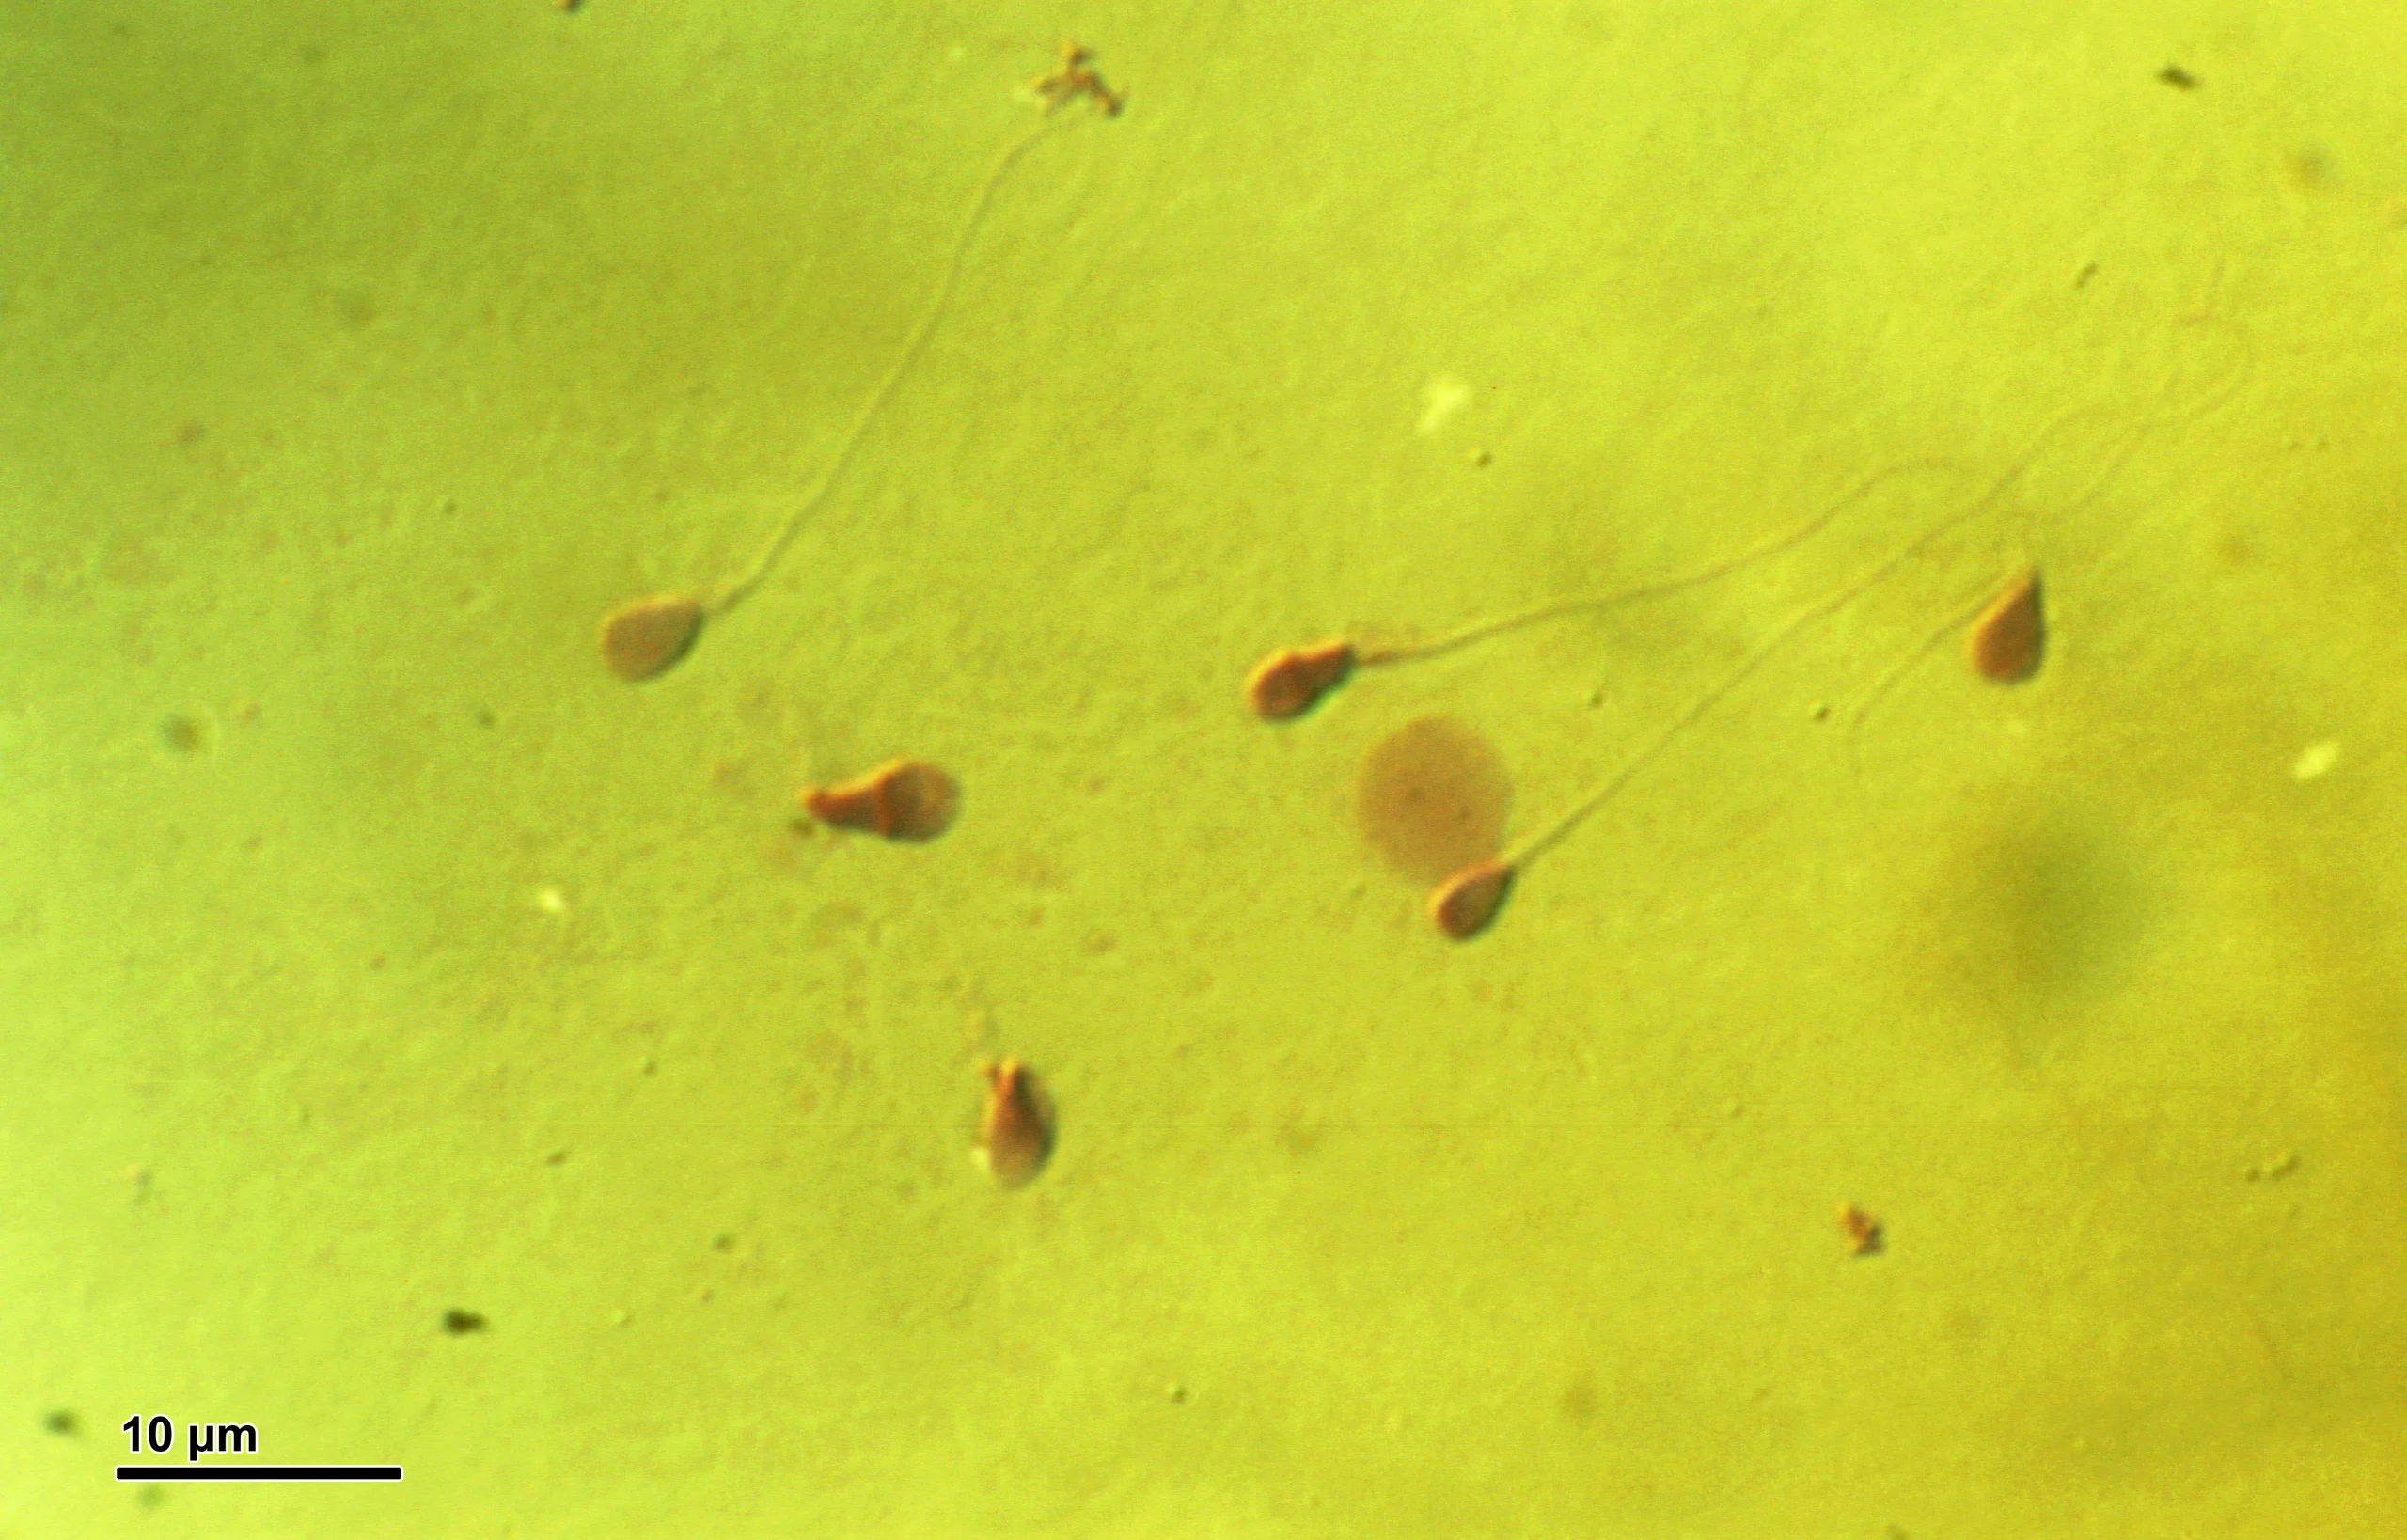
The genetic material in the sperm head matters too. DNA fragmentation means breaks in that genetic material. A routine semen analysis does not directly measure this damage: normal values for count, movement, and shape therefore do not reliably rule out increased DNA fragmentation.
Specialised additional tests are available. The EAU guideline recommends them particularly for unexplained infertility, recurrent pregnancy loss, or unsuccessful assisted reproduction treatment. The AUA/ASRM guideline does not recommend these tests as a routine part of the initial evaluation.
How useful a result is also depends on the test method and the individual situation. A value does not automatically explain the cause or reliably predict treatment success. Additional testing is useful when it can answer a specific question and inform further counselling. For an overview of the standard test, see semen analysis and understanding the results.
Why semen samples can vary
A sample is a snapshot. For a useful comparison, the circumstances matter too. A different period of abstinence or an incompletely collected sample can affect interpretation.
- Follow the laboratory's instructions for preparation and collection.
- Let the staff know if any of the ejaculate was lost.
- Mention infections involving fever in recent weeks and months.
- Be open about medications, testosterone products, and anabolic steroids.
- Ask your doctor when to provide a repeat sample and how to prepare for it.
A repeat test is often recommended after an abnormal result. The timing depends on the findings and any possible temporary influences. If a result is clearly abnormal, do not decide on your own to postpone further assessment for months.
For detailed guidance on sample collection, abstinence, and interpreting individual values, see the article on semen analysis.
What can affect sperm quality?
Poor semen analysis results can have very different causes. Lifestyle is part of the picture, but not every change is self-inflicted or can be corrected through habits. Hormonal, genetic, and anatomical causes also belong in an assessment.
Fever and significant heat exposure
Sperm production is sensitive to increased temperatures. Prolonged fever or repeated significant heat exposure can affect semen parameters. An effect may not be visible immediately and can persist for a while after the trigger has passed. The MSD Manual on sperm disorders describes this relationship.
You cannot calculate your chance of pregnancy from a single sauna session. If your results are abnormal and you are often exposed to intense heat, discuss ways to reduce that exposure temporarily.
Smoking, alcohol, exercise, and weight
Smoking, heavy alcohol consumption, and significant excess weight are associated with less favourable semen results. Quitting smoking, exercising regularly, and eating a balanced diet are sensible starting points. However, they cannot promise better results or a pregnancy.
The aim is a realistic plan without blame. Male fertility and age explores the age connection; age, stress, and lifestyle covers other influences.
Testosterone, anabolic steroids, and medications
Testosterone from outside the body and anabolic steroids can strongly suppress the body's own sperm production. Testosterone is therefore not a treatment for improving male fertility. The EAU guideline specifically warns against this use when trying to conceive.
Other medications may also matter in an assessment. Bring a complete list, but do not change a prescribed treatment on your own. When symptoms or a suspected infection are involved, the focus is targeted diagnosis and treatment.
Do supplements improve sperm quality?
Many products promise better semen results or less oxidative stress. This means cellular stress caused by reactive oxygen compounds; antioxidants are intended to limit this damage. What matters, however, is whether treatment actually helps people, for example by improving the chance of a live birth. A plausible mechanism or a changed lab value is not enough.
The randomised SUMMER trial, published in 2025, analysed data from 1,171 men trying to conceive. The antioxidant supplement studied did not produce a statistically significant increase in the rate of ongoing pregnancies within six months compared with placebo. The earlier MOXI trial had also found no convincing benefit for the semen parameters studied.
Because the evidence is uncertain, the 2025 WHO infertility guideline makes no recommendation for or against antioxidants in men with abnormal semen parameters. Its evidence search ran through April 2024, so it did not include the later SUMMER publication. These findings do not support a blanket promise of improved fertility.
This does not mean a confirmed deficiency should go untreated. Supplements do not replace a diagnosis or treatment of an identifiable cause. If you are trying to conceive, advice agreed with your clinician and tailored to your situation is more useful than taking several high-dose products just in case.
Are sperm counts declining worldwide?
Large meta-analyses report a decline in sperm concentration and total count over several decades. Frequently cited studies include the work by Levine and colleagues in 2017 and their expanded 2022 analysis.
The interpretation remains debated: differences in the populations studied, regional gaps in the data, and variation in methods make sweeping conclusions difficult. A critical review in Nature Reviews Urology therefore takes a more cautious view of the global trend.
None of this provides a diagnosis for you personally. A possible population trend tells you neither what your own results are nor whether you can father a child. An individual assessment is more useful here than a headline.
When should you have a fertility assessment?
An assessment is usually recommended after twelve months of regular unprotected intercourse without pregnancy. If the person hoping to become pregnant is 35 or older, it is often worthwhile after six months. Known risks or symptoms may justify an earlier appointment. The CDC overview of infertility explains this guidance.
Examples include known testicular conditions, previous cancer treatment, or problems with erections and ejaculation. An assessment should consider both people. It starts with medical history and appropriate examinations; for the man, a semen analysis is usually included. Further steps depend on the findings.
If you are planning sperm donation or another route to starting a family, the waiting periods for unprotected intercourse are not a prerequisite for seeking advice. The tests you need depend on the route you choose. A good semen analysis replaces neither a discussion of your medical history nor targeted infection testing. The overview of health information for sperm donation can help you prepare.
For very low or undetectable sperm counts, the introduction to azoospermia is a useful starting point. If treatment becomes an option later, the articles on IUI, IVF, and ICSI explain the respective procedures.
Conclusion
Semen combines sperm cells with glandular secretions. Its volume and appearance can vary, and testing is needed to assess sperm quality more accurately. If you have symptoms, persistent changes, or difficulty conceiving, the findings can help you decide what to do next. For everyday purposes, remember that a larger volume, thicker consistency, or unusually white colour does not automatically mean greater fertility.
Learn more about semen and fertility
Test results, age, unusual everyday questions and taste: these articles explore the questions that interest you.