The global fertility crisis: why birth rates are falling
Many countries are seeing fewer children per woman, while some people have smaller families than they hoped for. A lower birth rate does not, however, prove that everyone is becoming biologically less fertile. This article separates demographic statistics from medical findings and explains how living conditions, age and health play a part.


At a glance
- The number of children per woman worldwide has dropped substantially: annual UN estimates show about 4.85 in 1950 compared with 2.25 in 2023.
- A low fertility rate measures a demographic pattern; it does not prove that individuals are becoming biologically less fertile.
- Family planning depends on personal wishes, relationships, age, health, child care, housing and financial security, among other things. These factors carry different weight across countries and life circumstances.
- The WHO statement that around one in six adults experiences infertility refers to their lifetime so far and does not establish a rise over time.
What do we mean by a fertility crisis?
The term fertility crisis often bundles together different concerns: fewer children are born, people have fewer children than they want, or pregnancy does not happen despite wanting a child. These questions are connected, but they are different. A low number of children per woman does not provide a diagnosis of a population's biological fertility.
In medicine, fertility usually means the ability to achieve a pregnancy. In demography, it describes observed births instead. Four terms help clarify what is being measured:
- Number of births
- The absolute number of children born within a particular period. It also reflects how many people are currently at the ages when starting a family is common.
- Birth rate
- Usually the number of live births per 1,000 people in a year. Because the denominator is the entire population, the population's age structure affects this rate.
- Total fertility rate, or TFR
- The calculated number of children a woman would have if the age-specific birth rates in a given year stayed unchanged throughout her reproductive life. It is a snapshot of birth patterns, not a prediction for one woman or a whole generation.
- Biological fertility
- The physical conditions that make pregnancy possible. Age, medical conditions and the fertility of both people involved matter; they cannot be determined from a national fertility rate.
The often mentioned replacement level of around 2.1 children per woman also requires context. Where mortality is low, it roughly describes one generation of parents being replaced by the next. Whether a population actually grows or shrinks also depends on its age structure and on immigration and emigration. A figure of 2.1 does not make a population immediately stable.
How much has the worldwide fertility rate declined?
The long-term decline is real. The United Nations' consistent annual estimates show the global total fertility rate falling from 4.852 children per woman in 1950 to 2.251 in 2023. That is a decline of around 54 per cent. In 1990, the comparable figure was 3.31. These figures use the World Population Prospects 2024 data revision, presented by Our World in Data.
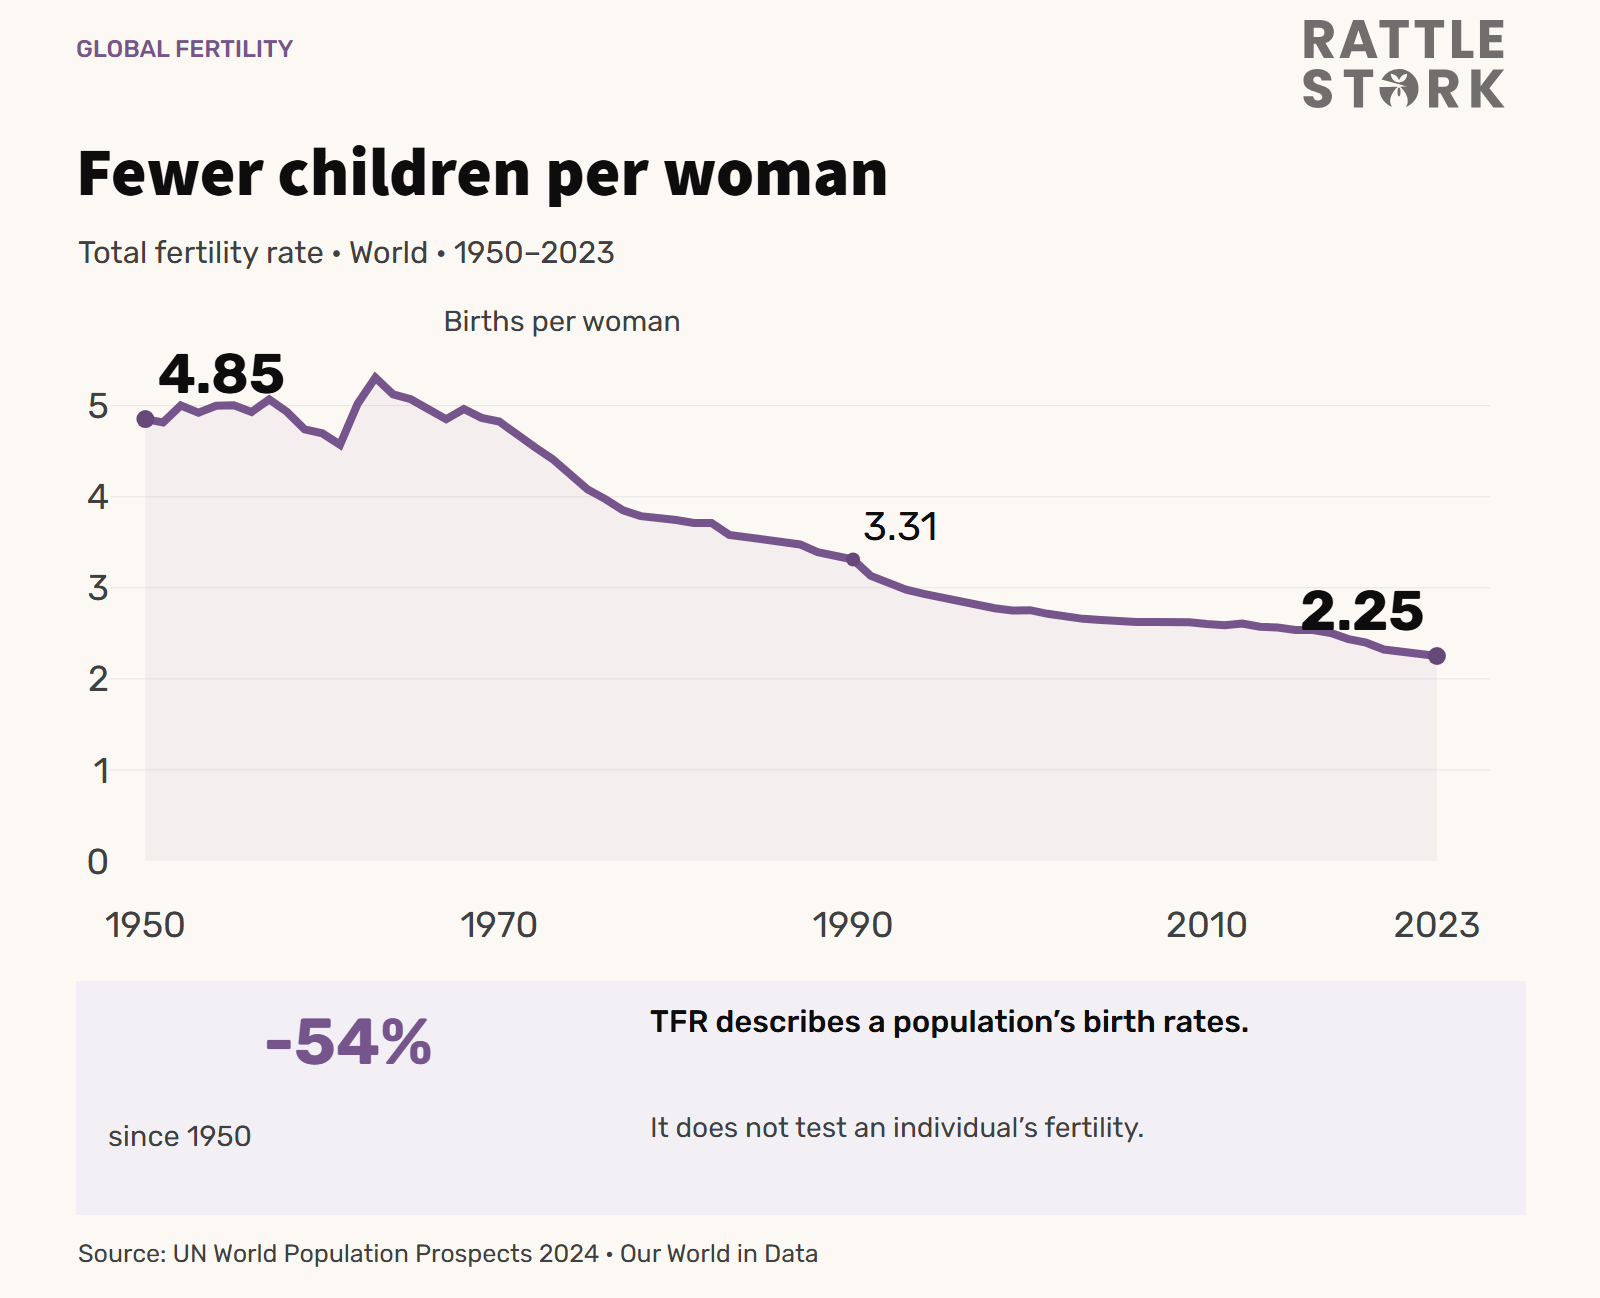
The graph presents historical annual estimates through 2023. For a meaningful comparison, use the same data revision and distinguish estimates from future projections.
When births happen also affects how the figures should be read. If people have children later, the TFR may fall at first, even though some of those births happen later on. A generation's actual completed family size can only be assessed once its childbearing years are mostly over. A decline in a yearly indicator therefore does not automatically mean every generation has fewer children by the same proportion.
Comparing countries and regions in a common data year
There are large differences. To keep statistical years consistent, every value below refers to 2023 and the same UN data revision. The chart shows seven selected countries alongside a world benchmark, rather than a ranking of all countries.
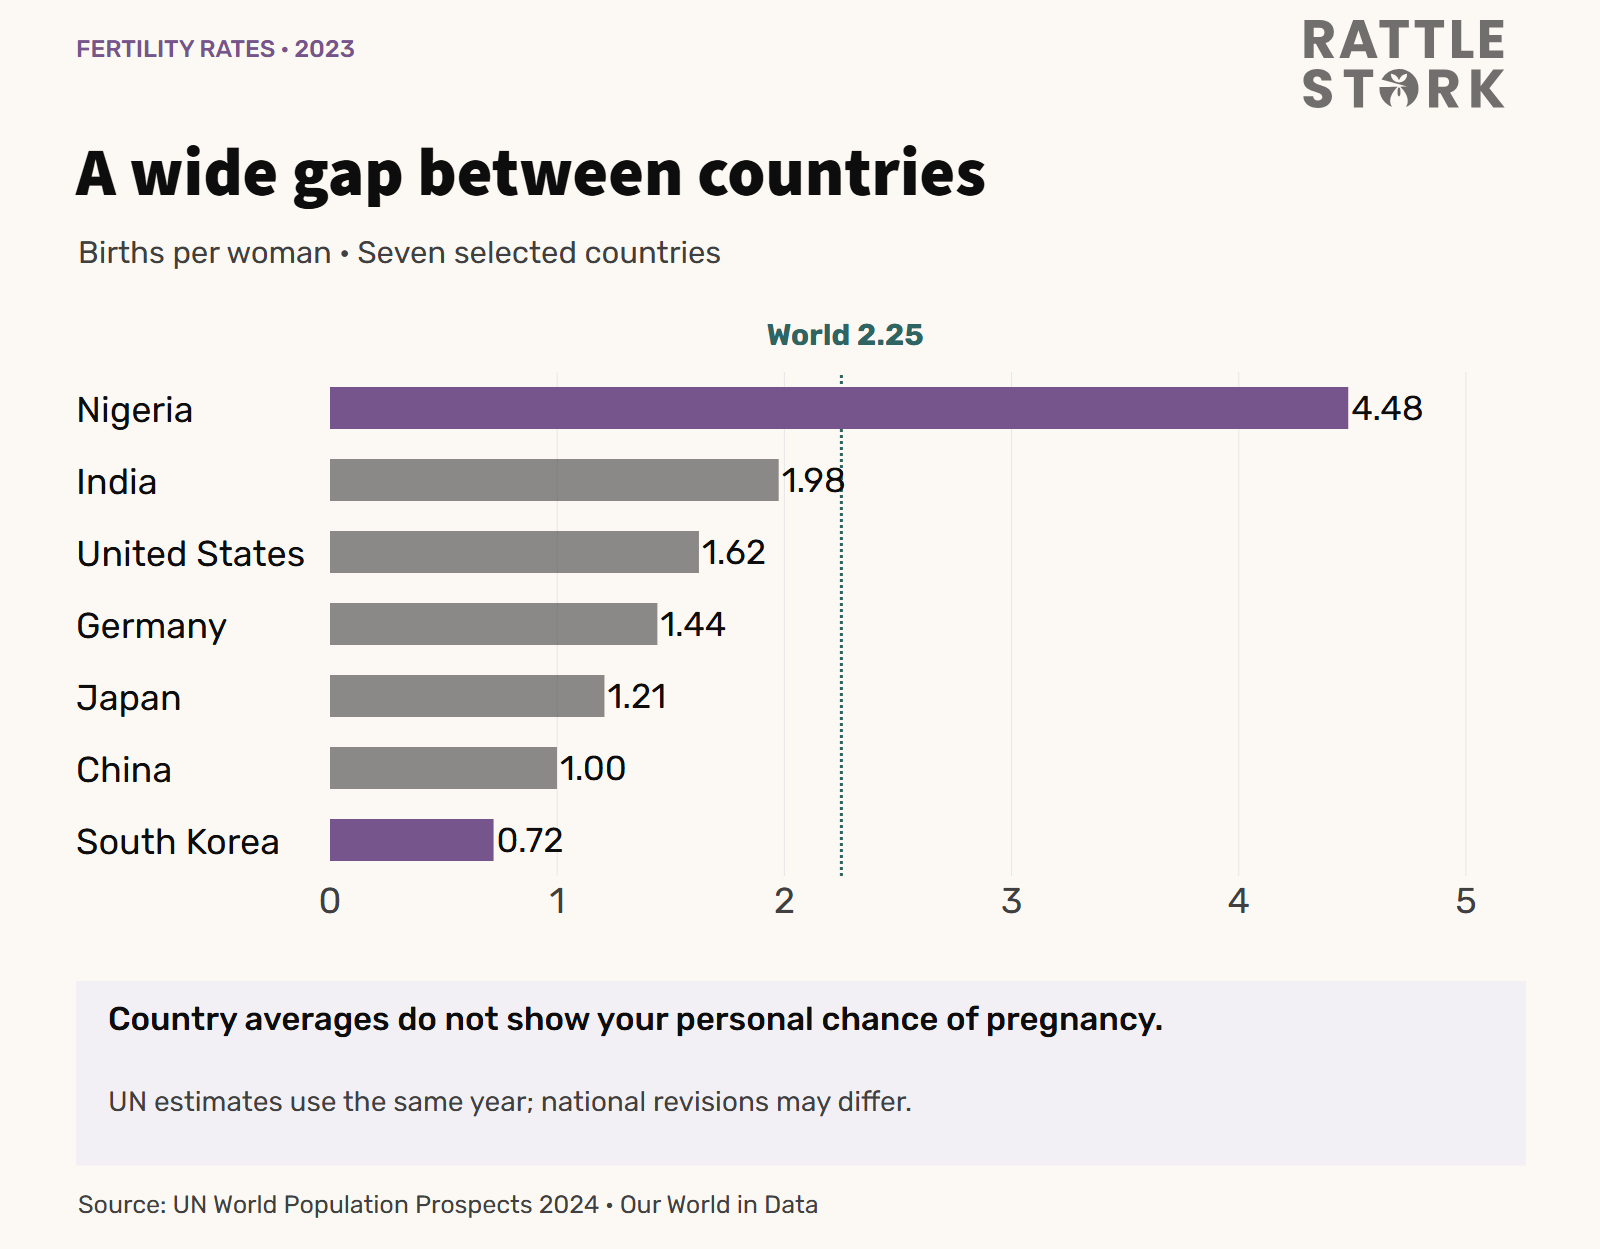
Selected values in children per woman, rounded to two decimal places:
- World: 2.25; Africa as a region: 4.06.
- Nigeria: 4.48; India: 1.98.
- Germany: 1.44; Russia: 1.45.
- Japan: 1.21; South Korea: 0.72.
- China: 1.00; Thailand: 1.21.
- Italy: 1.20; Spain: 1.21.
- United States: 1.62; United Kingdom: 1.56.
The underlying UN series makes this consistent comparison possible. Newer national publications may report different values, for example after revisions or for a more recent year. That is not necessarily a contradiction. Averages for countries and regions also conceal substantial differences within populations.
Why people have fewer children or wait longer
Family planning rarely has just one cause. Some people make a deliberate choice to have no children or fewer children. Others do not find a suitable partner, put off starting a family or have a smaller family than they would like. Which explanation matters most differs across countries, generations and life circumstances.
People who want children often face several practical barriers at once:
- Housing and living expenses: needing a larger home, covering ongoing costs and building financial reserves influence the decision to have a child or another child.
- Employment and income: temporary contracts, unpredictable shifts or worries about career penalties can make plans harder.
- Child care and time: dependable child care helps little if its hours do not match work and commuting time.
- Sharing care responsibilities: whoever handles most appointments, housework and child care has less capacity to take on more.
- Relationships and support: not having a stable relationship or having only a small support network can delay plans for a child.
- Expectations for the future: economic insecurity and concerns about the future can change what people want or slow their plans.
The 2025 UNFPA report draws attention to the gap between wishes and reality. In its survey of 14 countries, 39 per cent said financial constraints had influenced, or were expected to influence, their desired family size. These are self-reports from a limited set of countries, not a global breakdown of the reasons for all births that did not occur.
The survey cannot establish an overall ranking of social and medical causes.
Where biological limits come in
The later people try to have the children they want, the more biological limits can matter. This goes beyond planning correctly: some cannot start earlier, and others encounter health problems regardless of age.
With age, egg numbers and quality decline, and pregnancy risks change. Male age may play a part too, but follows different patterns with less clearly defined boundaries. An average effect of age is not an individual forecast. The articles about age and female fertility and how age affects sperm cover the basics.
Ovulation disorders, endometriosis, fallopian tube damage, reduced sperm production and other medical conditions can also make conception difficult. Better diagnosis can bring such problems into view. The number of diagnoses alone therefore does not tell us whether biological fertility is declining overall.
How common is infertility in reality?
Infertility is a real and widespread health burden. The WHO defines it as not achieving a pregnancy after at least 12 months of regular unprotected sexual intercourse. This definition does not tell people with known problems to always wait a year before seeking advice.
The frequently cited statement that about one in six adults is affected refers to infertility at some point in their lifetime so far. The pooled lifetime estimate is 17.5 per cent, with a 95 per cent confidence interval of 15.0 to 20.3 per cent. Its sources are the 2023 WHO analysis and the systematic review by Cox and colleagues, drawing on studies from 1990 to 2021.
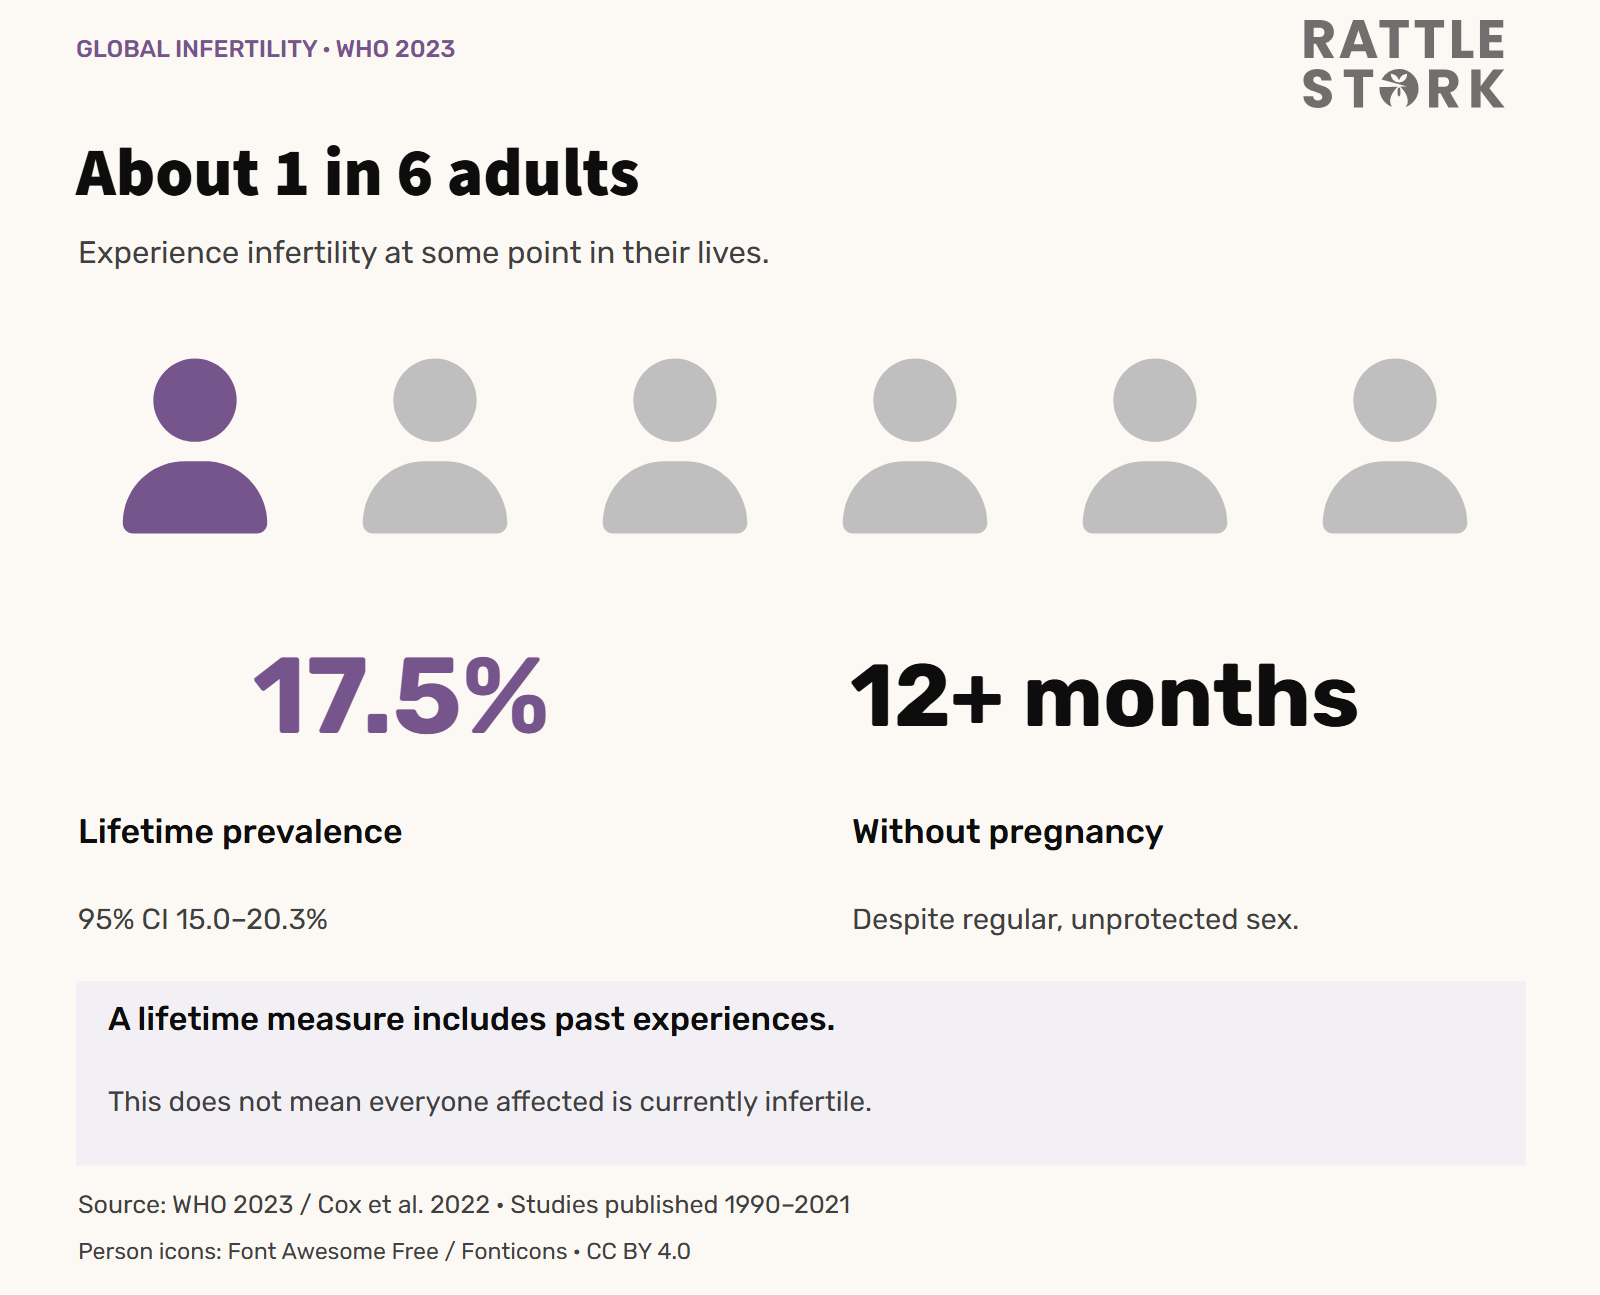
This does not mean all these people are currently infertile or that they are permanently unable to have children. The review also reports a period prevalence of 12.6 per cent for defined study periods. These are not before-and-after figures: different reference periods and study populations mean they cannot establish an increase. The considerable differences among the studies also matter.
Falling sperm counts: what the evidence shows and leaves open
A possible decline in semen quality has been discussed in research for years. A large meta-analysis by Levine and colleagues describes declining sperm concentrations and total sperm counts between 1973 and 2018 across the studies reviewed. This is a finding worth taking seriously.
It is not, however, a complete count of all men around the world. Semen samples are drawn from different populations, and recruitment, assessment methods and regional coverage vary. The review by Auger and colleagues explains these methodological limitations and considers which regional observations can be generalized.
Observed declines should not simply be dismissed. At the same time, a decline in a sperm measure is not equivalent to an equally large drop in the chance of pregnancy, nor does it explain a particular share of falling births. To establish those links, sperm measures, actual pregnancies and social conditions would need to be studied together.
Why the global population can still increase
A decline in children per woman does not immediately shrink the world population. In the same UN estimates, the global population grew from about 2.49 billion to 8.09 billion between 1950 and 2023 while the TFR fell substantially. The two measures describe different things.
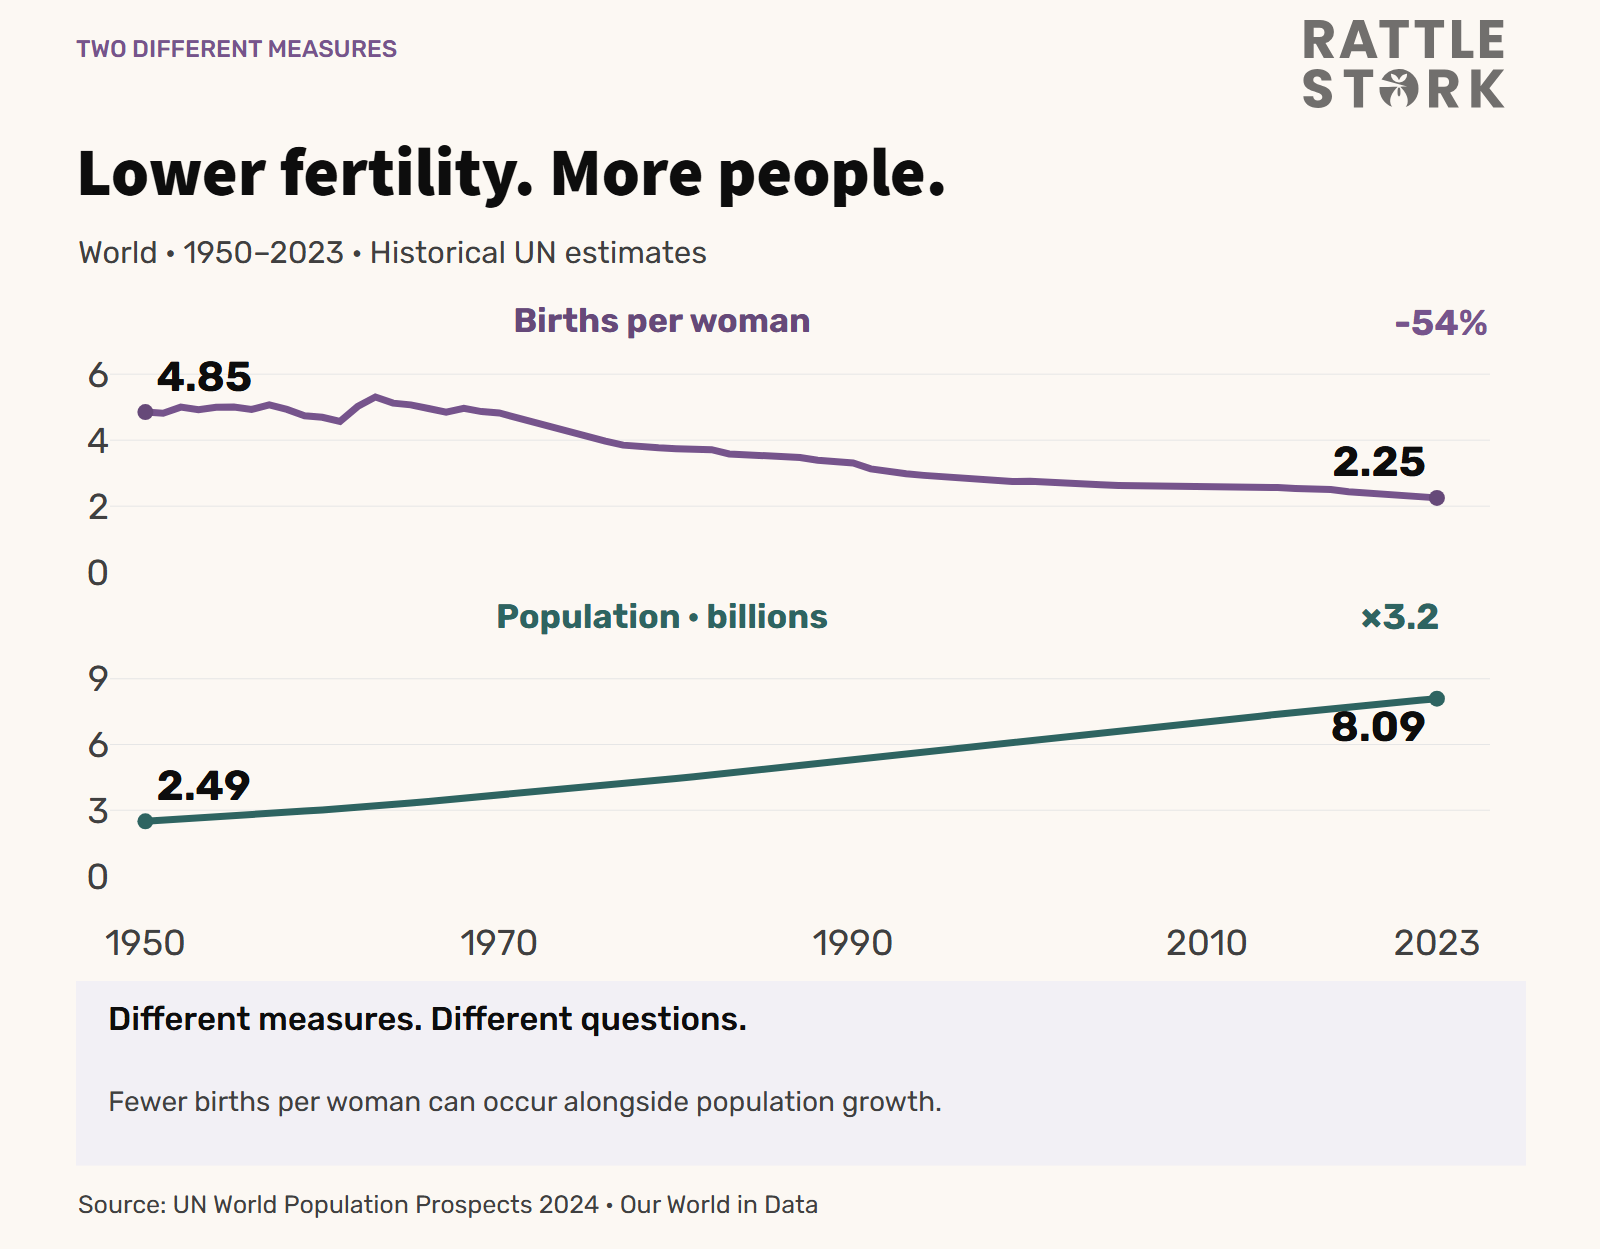
The number of births also depends on the size of the generation becoming parents. Deaths and life expectancy affect population size at the same time. Growth can therefore continue for a while even as children per woman decline. The 2023 global figure of about 2.25 also remains above the often used replacement benchmark of around 2.1. UN population data presented by Our World in Data.
What fewer births mean for population change
If younger generations stay smaller over a long period, the age structure changes. The extent of the consequences depends on the country, region and policy choices.
- Work and services: smaller younger generations may make recruiting skilled workers more difficult, including in nursing and other sectors that need large numbers of staff.
- Social protection: the balance between working people and retirees affects how pensions, health care and long-term care are financed.
- Regional infrastructure: some communities need fewer school spaces while needing more services suited to older people. Others can continue growing through inward migration.
- Adaptation: immigration, productivity, workforce participation and reliable infrastructure provide different ways to respond.
These consequences make the decline relevant to public policy. They do not impose an obligation on individuals to have children. Good family policy supports decisions people make for themselves, rather than making private life plans responsible for a target figure.
The fertility crisis: common myths and the facts
- Myth: COVID-19 vaccines explain declining births.
- The WHO finds no evidence that COVID-19 vaccines interfere with fertility. The long-term decline in demographic data also began well before 2020. An overlap in timing cannot establish causation. WHO information about COVID-19 vaccines.
- Myth: The pandemic explains all permanently low birth rates.
- Pandemic years can shift decisions and help shape short-term drops or later catch-up births. Lasting effects have to be examined by country and period. This explanation does not replace looking at changes over decades.
- Myth: Medical infertility explains the whole decline in births.
- Infertility matters, but birth numbers also depend on people's wishes, how many potential parents there are and their living conditions. Medical prevalence alone cannot explain a demographic time series.
- Myth: Environmental toxins such as BPA are the single cause.
- Environmental influences are among the questions studied in reproductive health research. They do not yield a simple explanation for differences between countries or for the entire decline in births. A plausible biological mechanism does not establish its share in a population trend.
- Myth: Higher education and employment inevitably prevent people from having children.
- Education and work affect life paths and may delay starting a family. Whether that means permanently fewer children also depends on support and the ability to combine work and family. The relationship is not inevitable for an individual.
- Myth: Only wealthy industrialized countries are affected.
- Fertility rates are declining in very different regions worldwide. The UN data show differences in pace and starting levels. A common trend does not mean the causes are identical in every country.
- Myth: A crisis is automatically followed by a permanent baby boom.
- Postponed births may happen later. A short-term increase, however, proves neither that people permanently want larger families nor that a long-term trend has reversed.
- Myth: Low birth numbers mean nobody wants children any more.
- Some people consciously choose to have no children or a smaller family. Others face practical obstacles that prevent or delay the family size they want. The two situations need to be distinguished.
What you can use for your own family planning
A worldwide statistic cannot tell you how your personal path will unfold. It is more useful to ask whether you want children, what conditions you need and which health concerns actually apply to your situation.
- Discuss wishes and circumstances: timing, sharing tasks, finances and support do not need to be perfect, but they should be talked about openly.
- Separate information from pressure: age matters biologically, yet a statistic cannot replace a discussion of your life circumstances.
- Support your health in sensible ways: not smoking, physical activity, a balanced diet and responsible alcohol use are reasonable foundations. They do not guarantee pregnancy or address every fertility disorder.
- Seek focused advice for symptoms: very irregular or absent periods, severe pain, known conditions or abnormal earlier findings call for an individual medical assessment.
- Know when to seek evaluation if pregnancy does not occur: with regular unprotected intercourse and no known risk factors, evaluation is recommended after 12 months for women under 35 and after six months from age 35. Over 40 or with known risks, earlier advice may make sense.
The 2026 ASRM guidance on fertility evaluation emphasizes that tests should be targeted and place as little burden on people as possible. If your family-building path requires donated sperm or medical support, for example, you do not first have to demonstrate unsuccessful attempts over those periods to seek counselling.
This does not support routine early testing for everyone. One laboratory result cannot reliably predict future fertility. If an evaluation is needed, potential factors on both sides should be considered. The findings determine which treatment is appropriate: intrauterine insemination (IUI), in vitro fertilization (IVF) and intracytoplasmic sperm injection (ICSI) are different procedures; testicular sperm extraction (TESE) is a surgical method of retrieving sperm.
For practical background, read about ovulation and the fertile window, IUI, IVF and ICSI. If you are planning further ahead, the overview of elective egg freezing, including its limitations, may also help.
How policymakers and employers can help
Helping people have the family life they want requires more than a single financial bonus. It means conditions they can rely on for years:
- Affordable child care with hours that fit actual daily life.
- Predictable working hours and a fair division of employment and care responsibilities.
- Accessible housing and less economic insecurity.
- Access to reproductive health care and clear counselling.
- Support for different family forms and people caring for relatives.
The OECD analysis of fertility and family policy discusses child care, working conditions and housing costs, among other factors. Individual measures have effects within a particular context; even extensive family policies do not guarantee a specific birth rate. They also have value in improving quality of life and freedom of choice.
Conclusion
Falling birth numbers in many countries and fewer children per woman worldwide are well-documented demographic developments. Health limitations and unfulfilled wishes for children are also real. None of these statements alone explains the others. Understanding the fertility crisis means considering birth patterns, biological fertility and the conditions for family life together, without treating them as equivalent. For your own plans, sound information, appropriate support and timely advice when needed offer more help than dramatic headlines.
Read more
More on the effects of age on fertility and planning a timeline for your own family.




