Can pre-cum cause pregnancy? Risks and next steps
Yes, pregnancy from pre-cum is possible, even without ejaculation in the vagina. Pre-ejaculate does not always contain sperm, but it can carry them. This article explains where the fluid comes from, how to put common situations in context and what to do after unprotected contact.


At a glance
- Pregnancy can happen without a visible ejaculation if fluid containing sperm reaches the vagina.
- Pre-ejaculate and semen are different fluids; sperm are not found in every sample, and the findings cannot give a reliable pregnancy percentage for a single encounter.
- Withdrawal is prone to errors; putting on a condom late does not protect against earlier contact.
- Sexually transmitted infections can be passed on even without ejaculation; condoms reduce many of these risks but do not remove them entirely.
- If there may have been contact without effective contraception, seek prompt advice about emergency contraception if you wish to avoid pregnancy.
Can you become pregnant without ejaculation?
Yes. A visible ejaculation in the vagina is not necessary for pregnancy. The important question is whether sperm reach the vagina and can travel from there to an egg that can be fertilised.
Contact with pre-ejaculate can allow this to happen too. Withdrawal or a condom put on too late poses a pregnancy risk when no other effective contraception is being used. Afterwards, it is usually not possible to know for certain whether sperm-containing fluid was released.
What is behind the question?
Questions about pre-cum often concern the whole situation rather than the fluid alone: a condom put on late, withdrawal, brief contact at the vaginal opening or sexual touching with fresh fluid on the fingers or genitals.
For pregnancy to occur, three things must coincide: sperm have to be present, they have to enter the vagina and the timing has to fall within the fertile window. Without that context, a percentage or someone else's account can look much more conclusive in hindsight than it really is.
What is pre-cum and where is it produced?
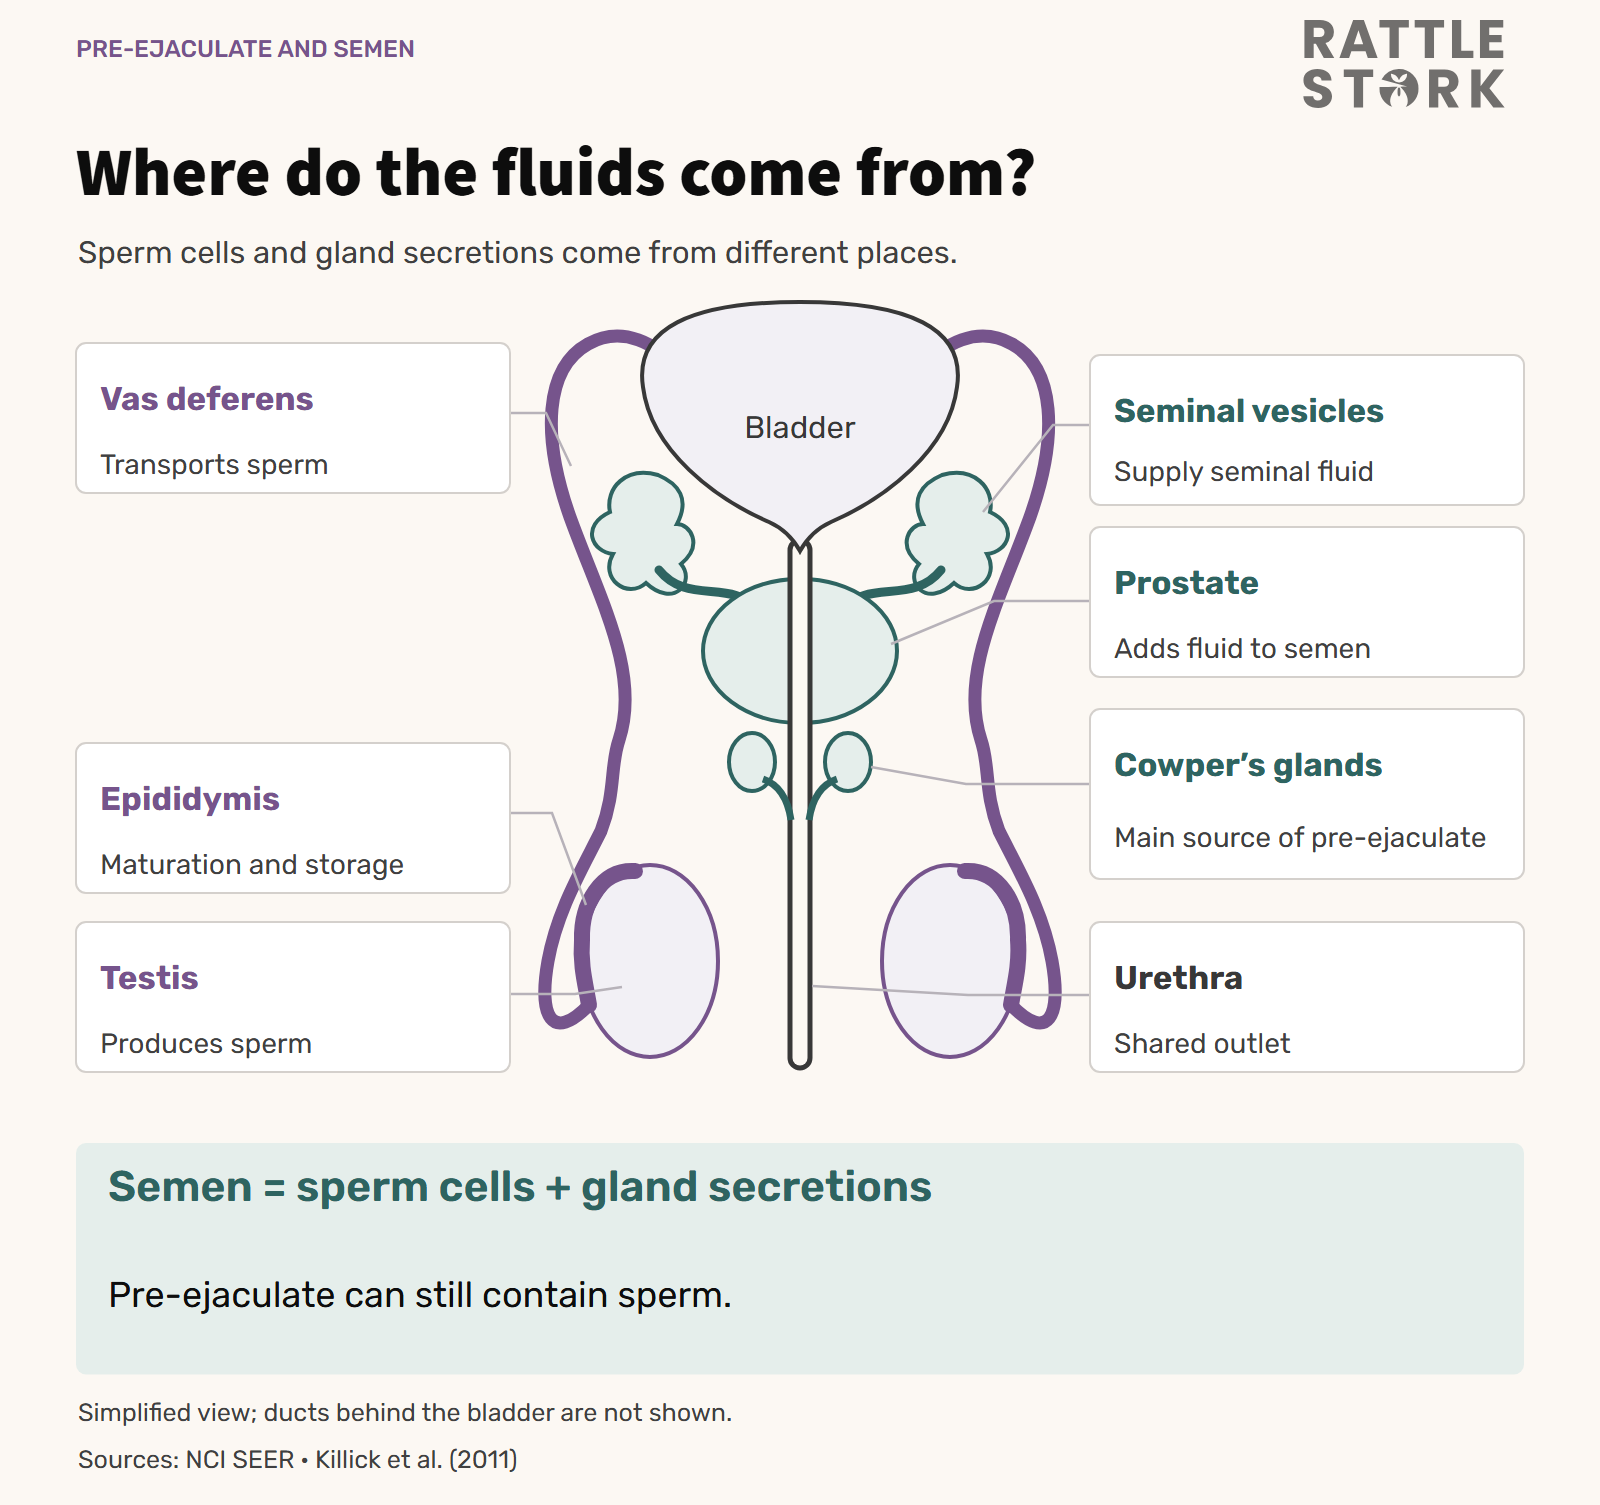
The medical term for pre-cum is pre-ejaculate. This fluid may come out of the penis during sexual arousal, before ejaculation. It comes mainly from the bulbourethral glands, also known as Cowper's glands, and helps to moisten the urethra.
Pre-ejaculate is not semen. Sperm develop in the testicles, and secretions from other glands are added during ejaculation.
- Testicles and epididymis
- The testicles produce sperm. Sperm mature and are stored in the epididymis before passing onwards through the sperm ducts, known as the vas deferens.
- Seminal vesicles and prostate
- Their secretions make up a large proportion of the fluid in semen. Semen therefore contains more than sperm and does not come solely from the testicles.
- Cowper's glands
- During arousal, these glands release a secretion that may emerge before ejaculation. They do not produce sperm themselves.
- Urethra
- This is the common route out of the body. Sharing a passage out of the body does not make pre-cum and semen the same fluid.
NCI SEER explains the anatomy of the glands involved and the sperm transport system.
Are there sperm in pre-cum? What the studies show
The findings are mixed. A widely cited study found sperm in some samples of pre-ejaculate, including motile sperm, meaning sperm that could move. Sperm content of pre-ejaculatory fluid (NCBI/PMC)
A pilot study published in 2024, involving 24 men who were experienced in using withdrawal, likewise found sperm in only some pre-ejaculate samples. It assessed sperm numbers and movement, not how many pregnancies actually occurred. Pilot study on sperm in pre-ejaculate (PubMed)
It is too simple to explain sperm in pre-cum as always being remnants of a previous ejaculation. Where the detected sperm come from is not fully established either. Passing urine after ejaculation therefore cannot guarantee that the next encounter's pre-ejaculate will be free of sperm. The AWMF guideline on non-hormonal contraception regards the evidence on this as insufficient.
The practical point is that appearance and sensation cannot tell you whether sperm were present. What matters is whether sperm-containing fluid could have entered the vagina and whether effective contraception was in place.
How likely is it to cause pregnancy?
There is no reliable percentage for pregnancy caused by pre-cum during one encounter. Studies examining sperm in pre-ejaculate do not measure how often a pregnancy actually results. Personal accounts cannot settle that question either, because it is rarely possible to reconstruct exactly what happened.
Figures for contraceptive methods in typical use are more helpful for understanding their reliability. Withdrawal is prone to mistakes in everyday use: around 20 in 100 women become pregnant in the first year of typical use. AWMF S2k guideline on non-hormonal contraception (March 2025)
That figure covers a whole year of using the method, not the risk from having sex once. It does not mean that pregnancy follows 20 per cent of contacts involving pre-cum. Our article on coitus interruptus explains more about withdrawal.
Fertile days and ovulation: why the timing matters
When sperm enter the vagina, the time before and around ovulation is particularly relevant. Sperm may survive for up to five days under favourable conditions. Sex a few days before ovulation can therefore result in pregnancy. See the overview of ovulation and fertile days.
If you use ovulation tests, our guide to LH tests is also useful: errors in testing or misunderstanding the time window can lead to an overly reassuring assessment.
These common circumstances can change how the situation is assessed:
- Fluid at the vaginal opening: fresh sperm-containing fluid may be relevant if it then enters the vagina.
- A condom put on late: it provides no protection before it is put on. Without another effective contraceptive method, the earlier contact matters when considering pregnancy.
- More than one round: semen remaining after an earlier ejaculation can play a part. A fresh condom is needed for the next round.
- Uncertain cycle timing: ovulation is often only estimated and may shift.
Putting common situations in perspective
You do not need a perfect record of events. A first assessment usually starts by identifying which of a few common situations applies.
- Withdrawal: the risk may be lower than with ejaculation in the vagina, but withdrawal alone remains prone to errors as contraception.
- A condom put on late: there is no condom protection before it is on. If no other effective contraception is being used, that earlier contact can already be relevant.
- Sexual touching or fingers: without direct contact between sperm-containing fluid and the vagina or vaginal opening, there is no plausible route to pregnancy.
- Brief vaginal contact: even short penetration without a condom may matter when no other effective contraception is in place.
- No penetration: the key is whether fresh sperm-containing fluid reached the vaginal opening directly or went into the vagina. More on pregnancy without penetration.
- Several encounters close together: what matters is whether sperm could have reached the vagina or its opening during any encounter. The number of rounds alone cannot give a risk calculation.
Condom mishaps can involve handling and the point at which the condom is put on. The article Condom broke explains what to do after a split, slipping or putting one on late.
The article How long do sperm survive? explains sperm survival in different conditions.
Pre-cum and sexually transmitted infections
People often think only of pregnancy when discussing pre-cum. In practice, another point may be just as important: unprotected contact can transmit sexually transmitted infections, whether or not ejaculation takes place.
Condoms reduce the risk considerably, but protection is not complete in every situation, such as contact with infected areas of skin. A clear overview is available at gesund.bund.de: Sexually transmitted infections.
Myths and facts about pre-cum
- Myth: Pre-cum is semen.
- Fact: Pre-ejaculate is a different fluid; sperm are not produced in pre-cum.
- Myth: Pre-cum always contains sperm.
- Fact: Not every sample contains sperm. If sperm are present, you cannot recognise this by appearance or confidently put it down to a previous ejaculation.
- Myth: Nothing can happen without ejaculation in the vagina.
- Fact: The key is whether any sperm reached the vagina, for example through early contact, a condom put on late or withdrawal that was too late.
- Myth: Withdrawal is nearly as safe as a condom.
- Fact: Withdrawal is much more prone to mistakes in typical use.
- Myth: It is enough to put a condom on at some point.
- Fact: Protection depends on the condom being correctly in place before the first genital contact and being used until the end.
- Myth: Brief contact does not count.
- Fact: Whether sperm reach the vagina matters more than the length of the contact.
- Myth: There is no risk outside the fertile days.
- Fact: The risk is usually lower, but both cycle timing and ovulation are often only estimated.
- Myth: Rinsing or showering after sex reliably reduces the risk.
- Fact: This is not a reliable method if fluid has already entered the vagina.
Reliable options for contraception
If uncertainty after sex repeatedly causes you distress, advice about contraception may help. Condoms reduce the risk of pregnancy and many sexually transmitted infections when used correctly from the start. A doctor or advisory service can discuss which additional method fits your daily life.

The AWMF guideline linked above offers a sound starting point for understanding errors and the reliability of non-hormonal methods.
A short check if you need advice now
The following information is particularly useful when seeking advice:
- Was there vaginal contact without a condom, or did fluid reach the vaginal opening?
- Could that fluid have contained sperm, for example pre-ejaculate or semen?
- Was another effective method being used, such as a correctly taken contraceptive pill or an intrauterine device (IUD)?
- How long ago did the contact happen, and is the stage of the menstrual cycle known?
These questions help during a consultation but do not allow a precise risk calculation. Vaginal contact without effective contraception can be a reason in itself to discuss emergency contraception. A roughly estimated ovulation date is not enough to exclude a risk.
What should you do after unprotected contact?
If you want to avoid pregnancy and there may have been vaginal contact without reliable pregnancy protection, ask a pharmacist or doctor about emergency contraception as soon as possible. Depending on its active ingredient, the emergency contraceptive pill may be used up to three or five days after sex, preferably as early as possible. A copper IUD may also be an option for emergency contraception. More information is available at familienplanung.de and in our article about the morning-after pill.
A urine pregnancy test is generally useful from the day your period is due. If you do not know when that is, test at least 21 days after the last unprotected sex. A negative test taken too early does not reliably exclude pregnancy; repeat it after a few days if your period has not arrived. NHS: When to take a pregnancy test.
Following possible exposure to a sexually transmitted infection, advice can help clarify which tests are appropriate and when. This depends on the infection and the time since contact. Symptoms such as pain, fever, unusual discharge, bleeding between periods or severe lower abdominal pain should be checked by a doctor.
Conclusion
Pre-cum can contain sperm and lead to pregnancy even if ejaculation did not occur in the vagina. That does not provide an exact probability for a single encounter. The type of contact, the contraception actually used and the timing all matter. Following a possible contraceptive mishap, timely advice is more useful than a supposedly precise percentage.
Read more
Further information on pregnancy risks, tests and the next steps after a contraceptive mishap.