Testosterone and having children: How TRT and anabolic steroids affect fertility
More testosterone does not automatically mean better fertility. Testosterone replacement therapy and anabolic steroids can substantially reduce sperm production even when sex drive, erections and muscle strength are maintained. The important factors are hormonal signalling inside the testicles and actual semen analysis findings. This article explains the connection, possible recovery and useful next steps if you want children now or later.


What to know
- Testosterone supplied from outside the body can sharply reduce sperm production or suppress it to azoospermia, when no sperm can be detected in a semen sample.
- Medically justified testosterone replacement therapy and anabolic steroid use for performance are different situations. Both can still reduce the hormonal signals sent to the testicles.
- Sex drive, erections, muscle mass and visible ejaculation do not reliably indicate whether you are producing enough sperm.
- Sperm production can recover, but the timing and extent differ from person to person. Discuss wanting children now or later early on, and do not change a prescription yourself.
Can testosterone cause infertility?
Yes. Testosterone supplied from outside the body can reduce sperm numbers enough to make natural conception much harder or impossible. That can happen even when you feel capable, have an active sex drive and have a reassuring testosterone blood level.
More testosterone circulating in the blood therefore does not automatically mean better fertility. Sperm production depends on hormonal conditions inside the testicles. With testosterone products, these can change quite differently from the blood reading. The EAU guideline on male infertility and AUA/ASRM guideline, updated in 2024, describe this relationship.
It does not follow that every man using testosterone is necessarily infertile, or that any impairment must last permanently. Actual semen findings, your history and the course over time are what count.
Your own testosterone, TRT and anabolic steroids are different situations
Testosterone is a hormone that the body naturally makes. Whether it becomes treatment or a fertility risk depends on the medical circumstances and how it is used.
- Testosterone produced by your body
- The testicles make most of it themselves. Coordinated hormonal signalling lets testosterone act throughout the body while maintaining the conditions for sperm production inside the testicles. A naturally normal level is different from one achieved by taking hormones.
- Testosterone replacement therapy, or TRT
- For a confirmed testosterone deficiency with compatible symptoms, prescribed replacement therapy can be appropriate. It aims to correct the deficiency and requires a sound diagnosis and regular follow-up. A medical indication does not, however, exclude an effect on fertility.
- Anabolic-androgenic steroids for performance enhancement
- Testosterone or related substances are used here mainly to increase muscle mass and performance. Use outside medical care, high amounts and combinations of several products differ substantially from monitored replacement treatment. Health risks and subsequent recovery are often harder to assess in these circumstances.
TRT and steroid misuse should therefore not be treated as interchangeable. In both situations, externally supplied androgens, hormones with testosterone-like effects, can suppress the signals controlling the testicles. Ordinary strength training is different. A muscular appearance establishes neither steroid use nor fertility. The EAU guideline on testosterone deficiency sets out the medical context.
Why the testicles need testosterone even though taking it can suppress sperm production
Hormonal control begins in the brain. Through the pituitary gland, two messengers enter the blood: LH, luteinizing hormone, stimulates testosterone production in the testicles. FSH, follicle-stimulating hormone, works with testosterone inside the testicles to support sperm production.
The testicles need a substantially higher testosterone concentration for this than the blood does. A blood test cannot simply establish whether enough hormone is available where sperm are made. Experimental research on testosterone inside the testicles helps explain this distinction.
When testosterone is supplied externally, the brain receives a signal that hormone levels are sufficient. This is called negative feedback. The pituitary releases less LH and FSH in response. Testosterone production within the testicles decreases, and some support from FSH is also lost. Sperm production can fall as a result, even while blood testosterone is normal or elevated.
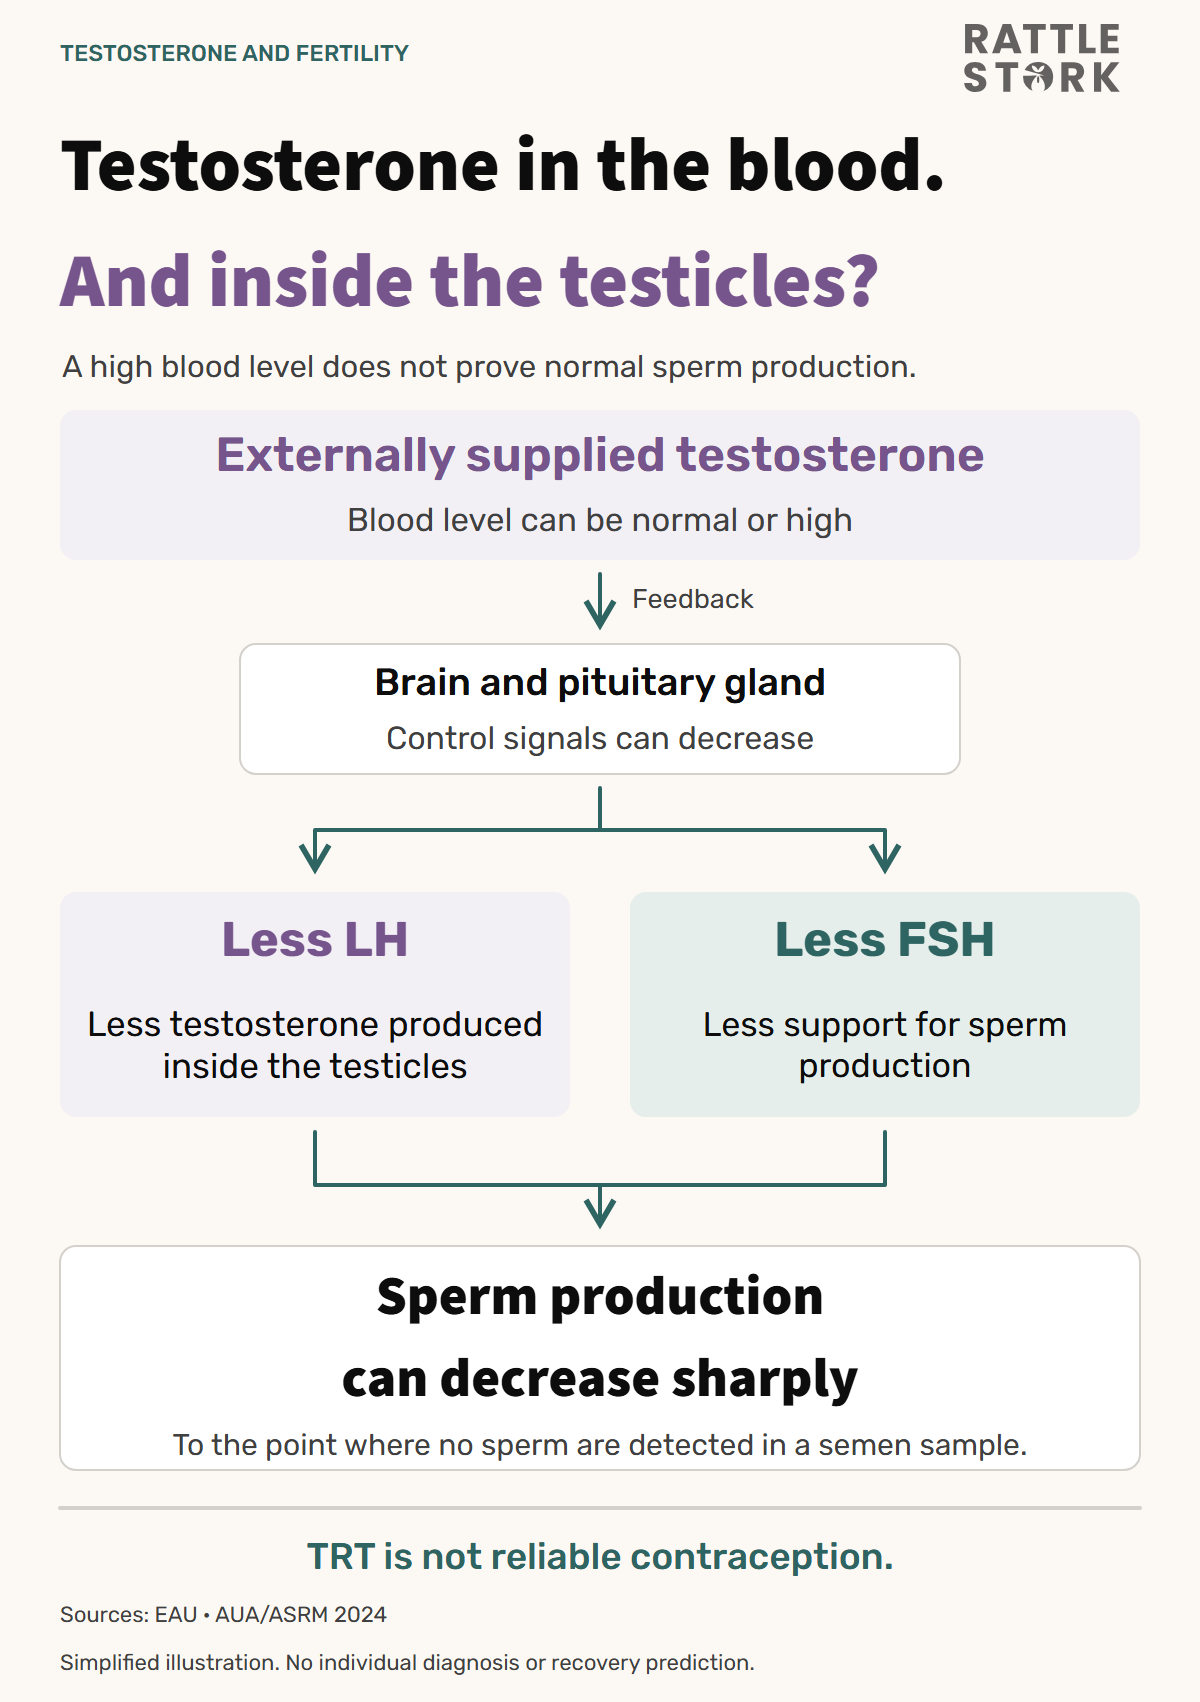
A sperm concentration below the reference range is called oligozoospermia. When no sperm can be detected in the semen sample, the finding is azoospermia. How you feel cannot establish either finding.
Does it matter whether testosterone is a gel, an injection or another preparation?
Prescribed testosterone gel also introduces testosterone from outside the body. Injections are therefore not the only form that matters for having children. The key issue is how the particular treatment affects hormonal signalling and sperm production.
Preparations differ in their duration of action and the fluctuations in blood levels, among other things. This does not establish an easy way to protect fertility. Switching preparations or taking a break on your own is not a reliable answer.
Small studies of short-acting testosterone delivered through the nose have reported more favourable semen findings. The AUA/ASRM guideline discusses this research, while emphasizing the limited data on preserving fertility over the long term. These initial results therefore do not guarantee that you will remain able to conceive during treatment.
Why sex drive, erections and ejaculation are not fertility tests
Sexual function and sperm production are related without being the same thing. Testosterone can influence desire and sexual experience while sperm numbers decrease sharply. A good erection does not rule out abnormal semen findings.
Visible seminal fluid also usually remains. It comes largely from glands such as the prostate and seminal vesicles; sperm represent only a small portion. An ejaculation that looks normal may therefore contain very few sperm or none at all.
Muscle mass, beard growth and feeling strong are no more conclusive. To know what is happening with sperm production, you need a semen analysis. This laboratory test gives more information than the appearance of semen or a single testosterone result. Even an unremarkable semen analysis does not guarantee pregnancy, however.
What a low testosterone result means for assessment
A low testosterone measurement does not automatically mean you need TRT. Fatigue, reduced desire and declining performance can have many causes. A deficiency is assessed using relevant symptoms and confirmed laboratory results, rather than one reading or an online questionnaire.
In the initial assessment, testosterone is generally measured in the morning while fasting; a low finding is confirmed before starting therapy. LH and FSH help determine whether the cause is mainly in the testicles or in the higher-level hormonal control. Illnesses, medications and other possible influences are also considered. The EAU guideline on diagnosing testosterone deficiency describes this approach.
If you already use testosterone, the timing and interpretation of tests require different considerations. Tell the clinician which preparation you use and when you last used it. If you want children, the assessment should establish what treatment could relieve symptoms while respecting your family plans.
Wanting children now or later: When to discuss it
If you want to conceive now, testosterone use belongs early in your medical planning. The AUA/ASRM guideline generally advises against prescribing exogenous testosterone, meaning testosterone from outside the body, to men interested in current or future fertility. It is particularly unsuitable for improving fertility when having a child is an immediate aim.
For children contemplated only in the distant future, the guideline discussion describes an individual assessment after counselling about the effects on sperm production and possible later recovery. This does not assure you that fertility will be preserved or return by a date you choose.
It helps to be concrete about timing: Do you plan to start trying in the foreseeable future, or would you like to keep the possibility open for later? Both merit a conversation before treatment. If you are already taking TRT, arrange a coordinated review rather than stopping it yourself.
TRT is not reliable contraception. Sperm production is not completely suppressed in every man. If pregnancy is not wanted, an appropriate contraceptive method is still needed. The Society for Endocrinology guideline explicitly points this out as well.
Fertility preservation before treatment: Should you freeze sperm?
Before planned testosterone therapy, discussing a baseline semen analysis and sperm freezing can be useful. This cryopreservation may allow later fertility treatment if few or no sperm are detectable in semen during use.
Whether this precaution is appropriate depends partly on your earlier semen results, diagnosis and family plans. Sperm freezing is not required for every man and does not guarantee a future child. Still, it is worth discussing before the first use rather than waiting until sperm production is already suppressed. The specialist overview Clinical Management of Male Infertility describes the option in the context of testosterone replacement therapy.
After TRT or anabolic steroids: Can sperm production recover?
Sperm production can recover after externally supplied hormones are discontinued. That does not mean everyone follows the same course, or that a short pause ensures normal results. The AUA/ASRM guideline describes recovery that may be prolonged; semen results remain impaired in some men.
Three questions need to be distinguished: Does hormonal signalling resume? Are sperm produced again? And are semen findings, together with other fertility factors, sufficient for a pregnancy? These milestones do not automatically occur together.
In men using anabolic steroids, the HAARLEM study showed that blood testosterone and sperm production may recover at different speeds. It followed men using androgens for non-medical purposes. Its results cannot be extended to every course of TRT or treated as your personal recovery timetable.
Age and length of use may also contribute. A clinical study by Kohn and colleagues found these associations in men receiving specialist hormonal treatment after testosterone was stopped. This retrospective investigation of a selected group does not predict how quickly a particular man will recover without treatment.
Interpretation also considers findings before use, prior steroid cycles, the preparations involved and additional reasons for impaired fertility. Without a baseline semen analysis, it is often difficult to separate out what was already present. A previous pregnancy also cannot prove that today's sperm production is unchanged.
What to tell your clinician about anabolic steroid use
After non-medical use, the history is often less clear than with documented TRT. Multiple substances, changing combinations, repeated cycles and uncertain contents complicate assessment. Provide the most accurate account you can, even if you cannot identify all the products or amounts.
Include products taken alongside steroids or as post-cycle therapy. These are intended to restart hormonal signalling after a steroid cycle. Such self-treatment does not prove that hormonal control has recovered or that enough sperm are present.
Medical support also makes sense if symptoms develop after stopping, including a substantial loss of sex drive or marked low mood. The Society for Endocrinology's 2026 position statement discusses these symptoms and uncertainty around recovery. You do not need to minimize your use to get help. The EAU guideline addresses anabolic steroids as a distinct influence and notes the limited evidence on treatment afterwards. The article on alcohol, nicotine, cannabis and fertility explains other substances and possible accompanying factors.
Which investigations help when you want children?
Contact a urologist with expertise in andrology. Andrology includes the assessment of male hormones and fertility. When testosterone or anabolic steroids are already a known factor, an early assessment is useful; you do not need to wait through a long period of unsuccessful attempts.
Medical history and physical examination
Important details include products, duration of use, most recent use, earlier cycles and additional substances. Packaging or photographs can help. Previous testicular problems, operations, illnesses and pregnancies also form part of the conversation. A physical examination complements laboratory results.
Semen analysis shows the current picture
This laboratory examination measures sperm number and movement, among other things. Abnormal results are often checked with a further sample, because semen findings can vary. The semen analysis guide explains preparation.
If no sperm are found, the result needs careful confirmation and interpretation. Hormonal suppression may explain azoospermia during testosterone use, but other causes must not be missed. Azoospermia alone does not prove permanent infertility.
Hormonal tests help narrow down the cause
Depending on the circumstances, testosterone, LH, FSH and potentially other tests can be helpful. Suppressed signalling during ongoing treatment is interpreted differently from signalling without externally supplied hormones. Also discuss when blood should be collected in relation to using the preparation.
These steps follow the basic approach of the EAU guideline for investigating male infertility. Additional tests are guided by the actual findings. Not everyone automatically needs all genetic investigations or imaging. The article on male infertility reviews other causes.
Treatment: Plan for symptoms and children together
Do not change prescribed testosterone treatment on your own. What comes next depends on why it was prescribed, the semen results and how soon you hope to have children. Sometimes the first step is an agreed treatment adjustment with follow-up testing.
For certain hormonal conditions, medications prescribed by a clinician can stimulate the body's own testicular function. This includes selected uses of gonadotropins, signalling hormones such as hCG or FSH. Other medications act on hormonal feedback. Suitability depends on the cause: a primary testicular disorder does not respond in the same way as a lack of control signals.
The AUA/ASRM guideline describes options for selected patients and the limited evidence. This does not establish a universal add-on program for every TRT prescription or instructions for self-treatment. Additional hormones also do not guarantee continued sperm production during testosterone use.
If findings remain impaired, assisted reproduction options may be discussed. Whether available sperm can be used and which procedure makes sense depend on the whole situation. A possible option is ICSI, which places a single sperm directly inside an egg. The timing of care for both partners should be coordinated rather than basing all planning on one testosterone measurement. Discuss together how long it is medically reasonable to wait and which options deserve early discussion.
Conclusion
More testosterone in the blood does not automatically mean better fertility. Testosterone supplied externally can suppress sperm production despite good sex drive and normal ejaculation. For children now or later, early andrology advice, semen analysis and treatment that considers symptoms and family planning together can help.
Making sense of sperm production and test results
Read more about semen analysis, other causes of male infertility and what azoospermia means.




