Which position helps you get pregnant? Sex positions, timing, and myths
Missionary, cowgirl, or doggy style: there is plenty of advice about positions when you are trying to conceive, but no proven advantage to any particular one. How plausible are the theories about gravity and penetration depth? Here you will find the main positions explained, what studies actually show, and what matters for timing and after sex.


At a glance
- No sex position has been shown to be better than others for getting pregnant. Choose a position that feels comfortable and does not hurt.
- Gravity and penetration depth can affect where semen is deposited. They have not been shown to result in more pregnancies.
- The days before ovulation and regular sex matter more when trying to conceive than a particular angle.
- Semen leaking out and urinating after sex do not rule out pregnancy.
Is there a best position for getting pregnant?
Based on current knowledge, there is no medically recommended best position. The American Society for Reproductive Medicine, ASRM, finds no proven conception advantage to a particular sex position or to resting longer afterward. ASRM: optimizing natural fertility
Your choice can still make a difference to you as a couple: when vaginal sex with ejaculation inside the vagina is comfortable and manageable, having sex regularly is often easier. That practical benefit is different from claiming that a particular angle directly increases the chance of fertilization.
What happens to sperm after sex
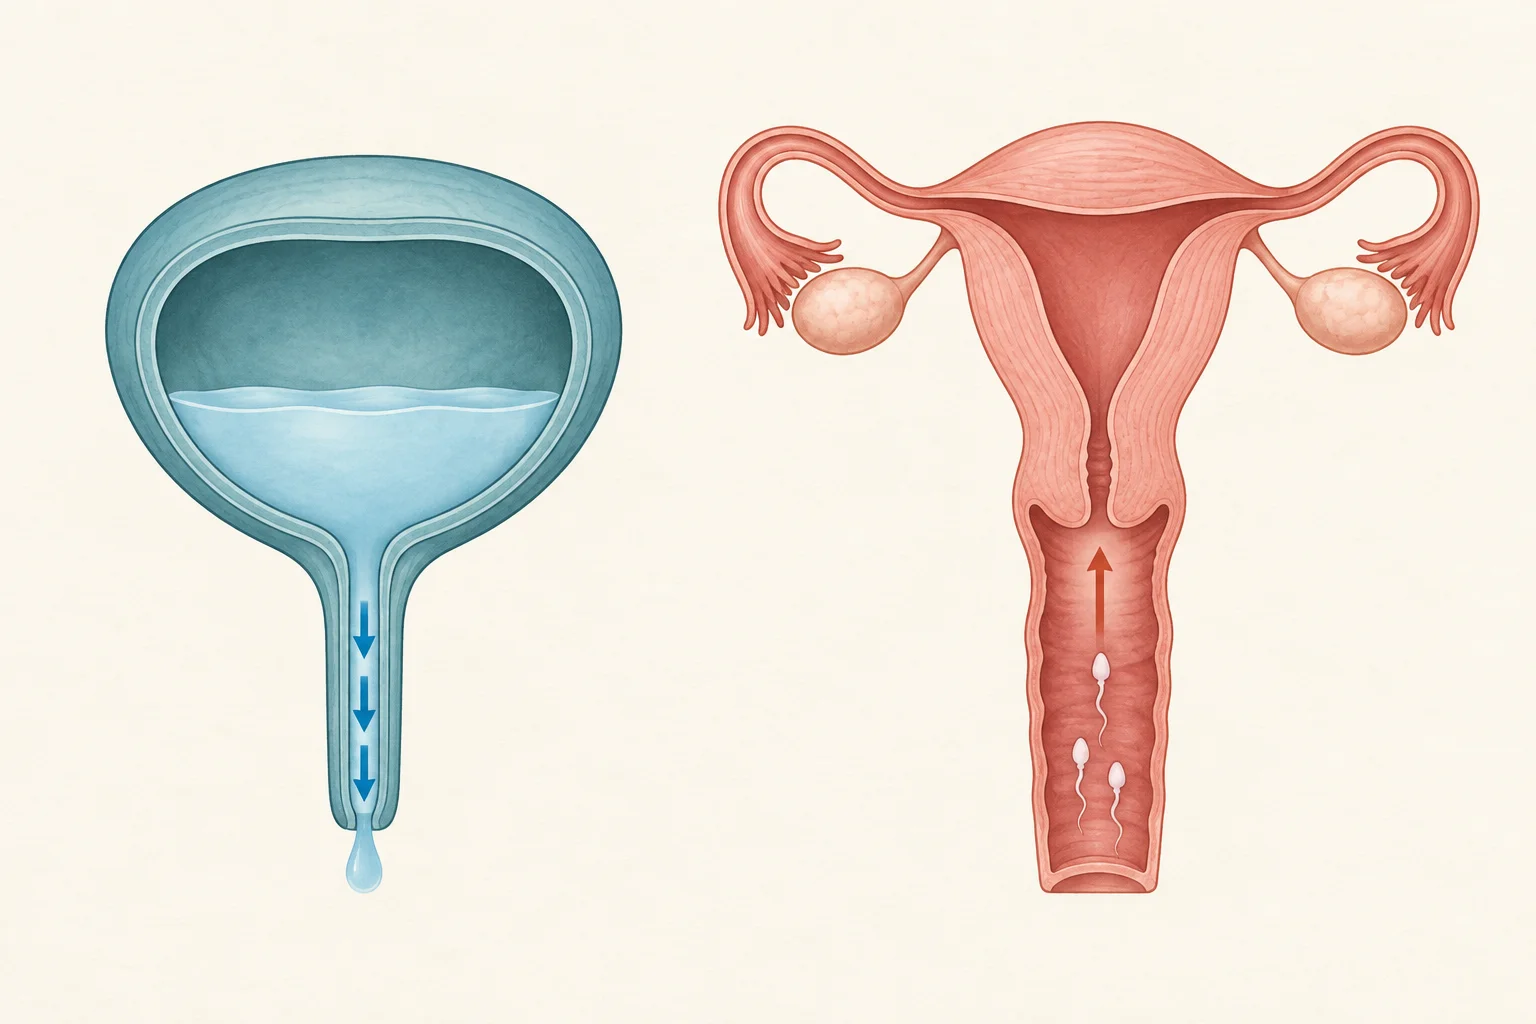
When ejaculation occurs inside the vagina, semen is initially deposited there. Sperm that can move may then pass through the cervix into the uterus and continue toward the fallopian tubes. Fertilization can happen there if a viable egg is present. Only a small proportion of sperm get that far. familienplanung.de: ovulation and fertilization
The initial location of the semen is only part of the picture. Motile sperm, open fallopian tubes, and timing in relation to ovulation also matter. A position cannot fix problems along this route. If you want to understand the difference between semen, sperm, and sperm quality, see our guide to semen.
Gravity and penetration depth: what is behind the theories?
Lying down is supposed to keep more semen inside, while deeper penetration is supposed to shorten the journey: these are two common ideas. Both are plausible as physical mechanisms. The key question, though, is whether they actually lead to more pregnancies.
Gravity affects fluid, but does not explain the whole journey
Gravity affects where fluid flows. That is why you may notice more leaking out when you stand up. Sperm, however, do not simply move passively upward or downward. They enter cervical mucus, the mucus in the cervix. Their own movement and contractions of the uterus help transport them onward.
A 1996 study tracked labeled particles the size of sperm from the outer opening of the cervix and examined wave-like uterine contractions. The findings support the importance of the body's own transport mechanisms. However, the study examined particles and transport routes, not pregnancy rates with different sex positions. Kunz et al.: transport in the reproductive tract
What this means: Less visible leakage does not automatically mean a higher chance of pregnancy. Conception is also possible in the cowgirl position or while standing. You do not have to remain lying down.
Deeper penetration does not automatically mean more pregnancies
Deeper penetration can change where semen is released in the vagina. These structures can also change position: a small MRI study from 1999 showed changes in the vagina and the position of the uterus during arousal and penetration. It made physical processes visible, but did not examine a conception benefit from deep penetration. Schultz et al.: MRI images during sex and arousal
A shorter route to the cervix initially sounds helpful. But it has not been shown to produce more pregnancies when ejaculation occurs inside the vagina. There is no required penetration depth in centimeters. The penis does not need to touch or press against the cervix; having a smaller penis does not rule out pregnancy either.
How large could an advantage be?
The available data do not support a reliable ranking or percentage. A lack of evidence for a benefit does not prove that every conceivable effect is impossible. But to recommend a position, studies would need to show that it actually results in more pregnancies or births. Anatomical images and less fluid leaking out are not enough.
In practice: You can lie on your back or use a pillow if that feels good. You do not need to put up with pain. Choose a comfortable position and focus your attention on your fertile days.
Sex positions by name: the main options explained
Many names describe the same basic position or small variations. When discussing conception, this guide focuses on vaginal sex; a position from behind, for example, does not automatically mean anal sex. For an overview of what sex involves and the differences between sexual practices, see How does sex work?
- Missionary position
- One person lies on their back, with the other facing them from above. Eye contact and communication are easy. Leg position and support change the angle; body weight should remain comfortably distributed.
- Doggy style
- This means a position from behind, often kneeling, with the person in front supporting themselves on their hands or forearms. The angle can allow greater depth. Speak up early if you feel pressure or pain.
- Cowgirl or partner-on-top position
- The person with a vagina sits on top, usually facing the person lying underneath. This often makes it easier to limit penetration depth themselves. However, the knees and thighs carry more weight. Comfort also depends on flexibility, the surface, and support.
- Reverse cowgirl
- The person on top faces the opposite direction from the usual cowgirl position. This changes the angle and body contact, and makes direct eye contact harder. Slow, coordinated movements help when changing position. As with cowgirl, the knees and thighs may take more strain.
- Spooning
- Both people lie on their sides, one behind the other. The surface supports much of their body weight, and movements are often smaller. This can feel comfortable when you are tired or want less physical effort. Adjusting leg placement changes the position.
- Seated and lotus positions
- In a seated position, both people face each other, with one sitting on the other's lap. Lotus is a closer variation, often with the legs crossed. It allows plenty of body contact, but may require flexibility in the hips and knees, depending on how it is done. A comfortable seated position does not need a particular name.
- Edge-of-bed and butterfly positions
- In these positions, one person lies near the edge of a stable surface while the other stands or kneels in front of them. Butterfly often refers to this arrangement with one person lying on their back, legs raised or open. Height, support, and angle affect comfort; the name is not defined the same way everywhere.
- Standing position
- Both people spend most of the time standing. Height, balance, and support play a larger role than in positions where you lie down. Stable support can help; change position if it becomes tiring.
- Viennese oyster
- This usually means a missionary variation with the legs raised high toward the upper body. It can allow deeper penetration and requires more flexibility. You do not have to try or endure this position to become pregnant.
- Scissors position
- The term describes different positions with the legs offset to the side or interwoven. Some involve vaginal penetration, while others mainly involve external contact. The name alone therefore tells you neither exactly what is happening nor whether pregnancy is possible.
- Coital alignment technique
- This is a modified missionary position in which body alignment and contact focus more on external stimulation of the clitoris. It relates to making sex enjoyable, and is not a technique with a proven conception advantage.
- 69
- 69 means mutual oral sex. It is part of the range of sexual intimacy, but is not a position for vaginal intercourse. Oral sex alone does not cause pregnancy; sperm would also need to reach the vaginal opening or enter the vagina.
Names such as monkey style, pretzel, or spork do not have consistent definitions. Describe the body position you mean to each other instead. A shared understanding is more useful than knowing as many position names as possible.
Which position suits you?
You do not need to work through a list or keep changing position. One or two familiar options that can be adjusted to your needs are often enough.
- For less effort: Lying on your side can help because neither your arms nor your knees have to carry much weight for long.
- For control over depth: A position where the person with a vagina helps control movement and distance may be more comfortable, such as cowgirl.
- For eye contact and closeness: Facing each other while one person lies on their back or while seated often works well.
- For differences in height: A stable surface, a different seat height, or a pillow for comfortable support can make trying things easier.
A position from behind is often also suggested for a backward-tilted uterus. This is commonly a normal anatomical variation and, by itself, is usually not an obstacle to fertility. If pain or endometriosis is also present, the underlying cause matters. A particular position does not treat it. Cleveland Clinic: retroverted uterus
You do not need a medical reason to dislike a position. For more on arousal, communication, and taking things slowly, see foreplay and your first time. If you are already pregnant and want to find comfortable positions, see the separate guide to sex during pregnancy.
Orgasm, pillows, and sex selection: more theories
There are also common promises about orgasm and what to do after sex. These three do not hold up when their claimed benefits are examined:
- Raising your legs and putting a pillow under your buttocks improves your chances
- No additional benefit has been demonstrated for these routines. A pillow can, of course, make you more comfortable; there is no prescribed pelvic height or waiting period for natural conception.
- A female orgasm is needed for sperm to arrive
- Orgasm can trigger muscle contractions and has been studied as a possible influence on transport. This has not established a pregnancy benefit. Orgasm is not required for conception, and you do not have to time it to coincide with ejaculation.
- The position determines whether you have a boy or a girl
- There is no convincing evidence that position, penetration depth, or a particular sexual sequence can control a baby's sex.
The ASRM review considers these questions about position, behavior after sex, orgasm, and sex selection together. ASRM: recommendations for natural conception
Timing: when sex offers the best chance
The fertile window covers approximately the five days before ovulation and the day of ovulation itself. Sperm can survive for several days in favorable conditions; the egg can only be fertilized for a short time after ovulation. That makes the preceding days especially important. Waiting only for the supposedly exact moment of ovulation may mean missing good opportunities. familienplanung.de: the fertile days
A calendar gives an estimate, not confirmation of ovulation. Timing can shift even with regular cycles. Changes in cervical mucus and LH tests can offer additional clues, but trying to conceive does not need to become a minute-by-minute schedule. The articles on ovulation and LH tests explain more.
For example, if ovulation is expected over the weekend, sex in the preceding days may already fall within the fertile window. You do not have to wait until Sunday or for a positive LH test.
How often to have sex when trying to conceive
One practical approach is to have sex every two to three days throughout the cycle. That way you do not need to predict ovulation exactly. The NHS also gives this guidance. NHS: trying to get pregnant
If you are focusing on the fertile window, sex every one to two days is a common recommendation. Daily sex is also an option when there are no abnormal findings; saving up sperm for longer is usually unnecessary. ASRM: frequency when trying to conceive
What matters is that the frequency works for both of you. Different instructions may apply before providing a semen sample or undergoing treatment; discuss these with your clinic.
If every fertile day becomes an obligation, it is fine to simplify your plan. Missing one opportunity does not mean you have done the whole cycle wrong. Not getting pregnant immediately despite good timing is not proof that you chose an unsuitable position.
Lubricants: balancing comfort and conception
More time for arousal and a suitable lubricant can help with dryness. Some products impair sperm in the laboratory. However, observational studies of couples did not show a corresponding overall reduction in the likelihood of conception with lubricant use. Laboratory findings therefore cannot be applied directly to a single use during sex.
If you need lubricant, a product labeled for trying to conceive and tested for sperm compatibility is a reasonable choice. That does not mean it increases fertility. Do not use saliva or whatever oil you have at home as a supposed fertility trick. The different findings are described in the ASRM review.
When certain positions cause pain
You do not need to endure a painful position to get pregnant. Less depth, a different position, more time, or a break may help right away. Be as specific as you can about burning at the entrance, pressure deeper inside, or a pulling sensation with a particular movement. This helps with adjustments and any later medical assessment.
Recurrent or severe pain should be assessed by a gynecologist. Possible causes range from dryness and pelvic floor problems to infections or endometriosis. Changing position may alter symptoms, but does not replace an assessment. ACOG: pain during sex
If vaginal sex is barely possible because of pain or erection or ejaculation problems, you do not need to spend months trying different positions first. Seeking medical advice earlier may make sense. Intercourse is not required for sperm donation; for the separate question of vaginal insemination, see the guide to the cup method.
After sex: lying down and semen leaking out
It is normal for fluid to leak back out of the vagina after sex. It can contain semen, vaginal secretions, and sperm. The visible amount does not tell you how many sperm have already moved toward the cervix. A lot of fluid on the sheets therefore does not mean the attempt was unsuccessful.
You can remain lying down because it feels good, or get up because you have something else to do. When trying to conceive naturally, there is no proven minimum time you need to lie down after intercourse. Putting your legs against a wall, placing a pillow under your buttocks, or deliberately holding fluid in is not necessary.
Studies of rest after intrauterine insemination have had different results: a 2009 study found a benefit from lying down for 15 minutes, but a larger 2017 study did not confirm it. In this treatment, prepared sperm are placed directly into the uterus. These findings do not establish a rule about lying down after sex. During treatment, follow your clinic's instructions. Custers et al., 2009, van Rijswijk et al., 2017
The later process of implantation is separate and happens in the days after fertilization. Getting up immediately after sex cannot undo it.
Can I use the bathroom after sex?
Yes. Urinating after sex does not flush sperm out of the vagina and does not prevent pregnancy. Urine leaves the bladder through the urethra; the vaginal opening is separate. Peeing therefore does not empty the route sperm take toward the uterus. MedlinePlus: vaginal anatomy
If you need to urinate, go to the bathroom. Avoiding unnecessary delays when you need to go supports bladder health, although urinating after sex does not guarantee protection against urinary tract infections. Trying to conceive is no reason to put up with a full bladder. NIDDK: bladder health
Burning and frequent urges to urinate immediately after sex are not reliable signs of pregnancy. If these symptoms are your main concern, see the explanation of bladder symptoms after sex.
Showering, washing, and vaginal douching
You can gently wash the external genital area with water. The inside of the vagina does not need rinsing: douching can disrupt its natural flora and does not prevent pregnancy. No special cleaning routine is needed when trying to conceive either. Office on Women's Health: douching
If you do not want to become pregnant right now
The same reasoning works the other way around: standing sex, cowgirl, getting up, showering, or urinating do not protect against pregnancy. There can be a risk even without visible ejaculation; see the article on pre-ejaculate for more.
After unprotected sex or contraceptive failure, emergency contraception may be important. Get advice from a pharmacist or clinician as soon as possible. Depending on the active ingredient, an emergency contraceptive pill may be an option for up to three or five days after sex; taking it as early as possible matters. A copper IUD may also be an option for emergency contraception. Do not wait for symptoms or a pregnancy test. gesund.bund.de: emergency contraception
Reliable contraception is needed for future protection. The guide to using condoms correctly helps with common usage mistakes.
When to take a pregnancy test
A test immediately after sex cannot yet show whether it will lead to pregnancy. Most urine tests are useful from the day your period is missed. If you do not know when it is due, testing at least 21 days after the last unprotected sex is a useful guide. Follow the test instructions too. NHS: pregnancy tests
If an early result is negative and your period still does not arrive, repeating the test after a few days may help. The position, the amount of fluid that leaked out, or a feeling immediately after sex cannot answer this question. See Am I pregnant? for more.
When to seek a fertility evaluation
If pregnancy does not happen, there comes a point when an evaluation of both partners is more useful than another position tip. For regular unprotected sex, ASRM gives these guidelines:
- Under 35: An evaluation after 12 months without pregnancy.
- Ages 35 to 40: An evaluation after six months.
- Over 40: Prompt advice may be useful right from the start.
These ages refer to the person trying to become pregnant through sex. Earlier evaluation makes sense if periods are absent or very irregular, or if there is pain or a known condition affecting fertility. The same applies to suspected problems with sperm, erections, or ejaculation. Both partners should be involved from the outset. ASRM: evaluating infertility
A semen analysis can be just as relevant as investigating ovulation or the fallopian tubes. The assessment is not a judgment on your sex life. It aims to identify any treatable factor that may have been missed.
A simple plan without pressure over positions
- Choose one or two positions in which you feel comfortable and can communicate easily.
- Make room for regular sex without concentrating every encounter on one calculated ovulation day.
- Take dryness and pain seriously and adjust what you are doing instead of enduring a position.
- Afterward, do what feels comfortable: remain lying down, get up, or use the bathroom.
- Seek support in good time if pregnancy is not happening or sex becomes a persistent source of strain.
Intimacy can also happen without penetration or ejaculation. Not every encounter has to be an attempt. For a broader overview of preparing for pregnancy, see Getting pregnant: what can help.
Conclusion
There is a plausible physical basis for theories about gravity and penetration depth. So far, though, research has not shown that these mechanisms improve the chance of pregnancy. Choose a position you enjoy, have sex regularly during the fertile window, and seek medical advice in good time if needed. How deeply the penis penetrates, and whether you get up or use the bathroom afterward, do not need to become a performance test.
Read more
These articles help you identify your fertile days, understand implantation, and work out when to take a pregnancy test.