How to measure your penis: length, girth and common errors
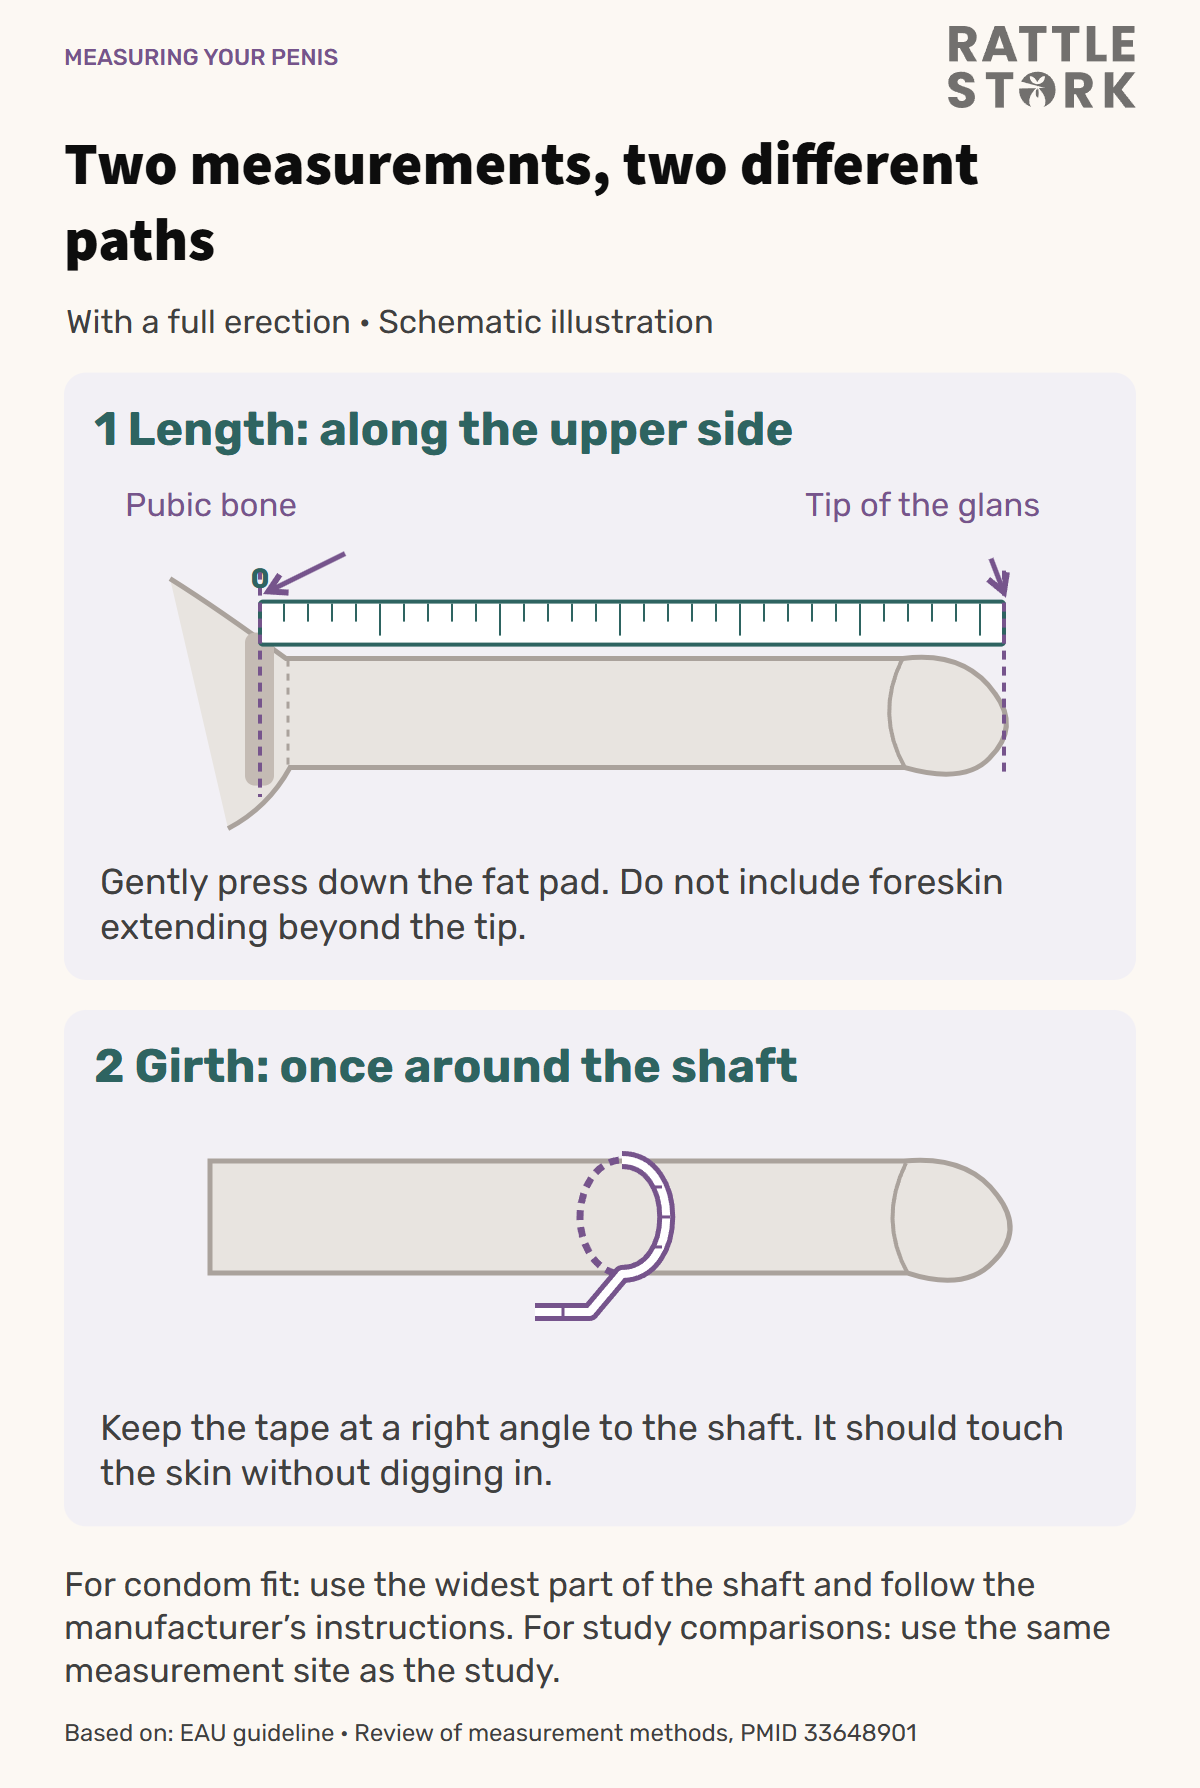
Measure penis length with a full erection, along the upper side from the pubic bone to the tip of the glans. For girth, take a soft measuring tape once around the shaft without digging into the skin. Stretched length measured while flaccid is a separate clinical measurement. If there is a curve, you also need to be clear about which path you want to measure.


At a glance
- Measure erect length along the upper side, from the pubic bone to the tip of the glans. Foreskin extending beyond the tip is not included.
- Measure girth by taking a tape once around the shaft without squeezing it. This figure is usually more useful than length for condom fit.
- Compare measurements only when the methods match. Stretched flaccid length is a separate clinical measurement.
- Weights and painful pulling do not improve a measurement. New changes or severe size anxiety need a different response from continually collecting millimetre readings.
Measuring length: from the pubic bone to the glans tip
For a clear measurement at home, use a rigid ruler with a clearly visible zero mark. Measure with as full an erection as possible and without pain. If the ruler has an unmarked edge before zero, position it so that the zero mark is at the starting point.
- Place the ruler along the upper side of the penis, the side facing your abdomen.
- Set the zero mark at the pubic bone. Gently press down the fat pad over it until you reach that firm reference point.
- Read the length in a straight line to the tip of the glans. Do not include foreskin extending beyond it.
- Keep your posture and measuring angle consistent. Do not force the penis straight or push it in another direction.
- For an initial guide, repeat the measurement on two or three occasions under similar conditions. A few comparable readings are more useful than the highest number from many attempts.
Using the pubic bone makes the starting point less dependent on skin and the fat pad. Measuring from visible skin instead describes visible length. That may help you track your own changes, but it is not directly comparable with a measurement from the pubic bone. Record the method when comparing results. EAU guideline on size measurement
Measuring girth: circumference rather than diameter
Measure girth with a soft tape during a full erection. Take it once around the shaft at a right angle to its length. It should touch the skin without digging in or compressing tissue. Alternatively, mark a non-stretch string where it overlaps, then measure that length against a ruler.
For finding a suitable condom, the widest part of the shaft is a practical reference point; also follow the manufacturer’s measuring instructions. To compare your result with a study, use that study’s measurement site instead. Some studies measure at mid-shaft, while others additionally measure nearer the glans. Girth measurements from different points on the shaft are not automatically comparable.
Girth, diameter and nominal condom width are different figures. Nominal width refers to a condom laid flat; it is neither your body’s circumference nor a personal target number. Condom sizes and nominal width explains how to move from a girth measurement to a suitable product and a fit check.
Why studies often stretch the flaccid penis
A study measurement is not necessarily taken during an erection. Researchers frequently use stretched penile length, or SPL: the length of the gently stretched, flaccid penis. This is a separate clinical measurement, not a stretching exercise.
A 2021 review covering 70 studies reported stretched measurements in 60% of studies and erect measurements in about 27%. Several studies measured more than one state. These percentages therefore do not describe separate groups and should not be completed into an exhaustive breakdown. Review of methods by Cakir et al.
SPL can help assess development; for condom fit, you mainly need erect girth. With a new curve, shape, angle and changes over time also matter. There is no single measurement for every purpose. Scientifically, a comparison becomes problematic when different states and starting points are treated as interchangeable.
Four measurements, four different meanings
- Unstretched flaccid length
- An easy reading to take, but a highly variable snapshot. Temperature, stress and circulation change it visibly.
- Stretched flaccid length
- The SPL commonly used in clinical practice. It provides an approximation that can be standardised and is used for age-specific reference values.
- Erect length
- Usually more intuitive for understanding your own size and sexual function, but dependent on erection quality and the measuring point.
- Erect girth
- More practical than length for condom fit and the sensation of width.
None is better for every purpose. Problems arise when a flaccid self-measurement is compared with an erect study figure, or a skin-based reading with a bone-pressed one.
Why a full erection matters for comparison
Erections are not identical every day. Sleep, stress, alcohol, medicines, mood and performance pressure affect firmness and fullness. Comparing a partial erection with a previous maximum measures current erection quality more than an anatomical change.
If erections become noticeably weaker over several weeks, constant measuring is not the best assessment. Blood pressure, medicines, metabolism, psychological context and possible vascular disease then need consideration. Understanding erectile dysfunction addresses that question more specifically.
Why unstretched flaccid length tells you little
An unstretched flaccid measurement is quick, but strongly affected by conditions. Cold can visibly retract the penis, while warmth lets it appear more relaxed. Exercise, anxiety and activation of the sympathetic nervous system also affect its state. The same person can therefore have quite different readings without an anatomical change.
Unstretched flaccid length can also be documented in a standardised examination. It is usually less informative for comparing men or considering sexual function, however. Casual changing-room comparisons are particularly misleading because temperature, perspective and erection response are all unknown.
The most common measurement errors
- Starting at the skin on one occasion and the pubic bone on another.
- Comparing a partial erection with a full one.
- Including foreskin or changing the endpoint.
- Compressing the fat pad with different amounts of pressure.
- Pulling to the point of pain for SPL or continually changing the force.
- Following a curve’s contour once and a straight line another time.
- Recording only the highest of many readings.
To track a change, document the method, state and date. One reading is rarely informative on its own. For a new change in shape, photographs with a full erection from the same angles are often more useful at a medical appointment than daily millimetre readings.
What stretched penile length means medically
For stretched penile length, or SPL, the flaccid penis is gently stretched to resistance and measured from the pubic bone to the glans tip. The examiner compresses the fat pad without causing pain. This measurement is used for developmental questions, possible micropenis, preparation for procedures and research, among other purposes.
SPL is particularly practical for infants and children because an erect measurement cannot be reliably planned and is not appropriate for a routine examination. The result is compared with age-specific reference data. An adult chart or a private photograph cannot replace that assessment.
The European Association of Urology recommends recording at least stretched length during a clinical size assessment. This describes the scope of examination, not a minimum anatomical size. Depending on the reason, additional flaccid and erect measurements may be useful or necessary before surgery. The guideline also notes that there is no complete international consensus on every detail. EAU guideline on penis size
Micropenis is diagnosed using SPL relative to age-specific reference data and the overall clinical picture, rather than a universal adult figure found online. Experienced professionals should therefore take this measurement in children and adolescents.
SPL and erect length are related, but not identical
It is often claimed that stretched length is virtually the same as erect length. The averages may be similar, yet an individual man’s measurements can differ considerably. In a study of 201 men with medically induced erections, stretched measurement underestimated erect length by an average of 2.64 cm, or just over 21%. There were also differences between examiners. Habous et al., 2015
This is not a general conversion factor. It shows that tissue elasticity, technique and the examiner matter. A fixed formula promising your exact erect length from your own SPL suggests greater precision than the method can provide.
450 grams of traction: a research figure, not home instructions
The frequently quoted figure of 450 g comes from an older clinical and technical study involving 55 patients. The authors used measurements and a mathematical model to examine how erect length could be predicted from stretched length. That does not turn the traction described there into a universal measuring instruction or a safe home standard. Chen et al. on predicting erect length
A clinical SPL measurement is not an experiment with hanging weights. Avoid jerking, forced stretching and pain. If you need a medically standardised reading, have a suitably qualified professional take it. A brief measurement cannot establish a safe setting for a penis extender either: medical traction is a different application with its own treatment plan.
How do you measure a curved penis?
For length along the upper contour, a flexible, non-stretch tape can follow the curve. A rigid ruler instead measures a straight projection. Contour length cannot be directly compared with a straight ruler measurement. Clinical comparisons follow the examination protocol being used. To track changes, choose one method and keep using it.
The curvature itself is better assessed through standardised photographs from several views or a urological examination. An angle-measuring app or a protractor can provide only a rough estimate at home. Diagnosis and treatment decisions do not depend on a self-measured angle alone.

Congenital curvature or Peyronie’s disease?
A stable curve present since puberty, without lumps or pain, can be congenital. Many mild curves are normal variations. Peyronie’s disease, by contrast, is an acquired change in the tunica albuginea. Possible features include a plaque you can feel, a new or increasing bend, indentations, shortening, pain or erection problems.
The EAU distinguishes an active phase, when pain and shape can still change, from a stable phase. This distinction matters because certain procedures can only be sensibly planned once the condition is stable. EAU guideline on penile curvature
A new curve should not simply be measured for months. An early urological assessment helps establish whether the cause is Peyronie’s disease, an injury or something else.
What a urology appointment assesses
Assessment covers changes over time, pain, erection function and whether intercourse is possible. The doctor examines the penis for plaques and assesses its erect shape, using either good personal photographs or a medically induced erection. Ultrasound can add information in certain situations, but is not automatically needed for every mild curve.
Useful details for the appointment include the approximate onset, subsequent changes, pain with erections, erection problems, medicines, previous injuries or operations, and exactly what no longer works during sex. Standardised photographs from the same views can show progression better than changing the angles every day.
Treatment addresses a functional situation rather than a photograph. Disease phase, pain, erection function and limitations during sex together determine whether observation, non-surgical treatment or a later procedure is appropriate. Measurement records the baseline; it does not replace specialist counselling.
When measuring helps, and when it increases worry
Standardised measurements are particularly important when micropenis is suspected, before reconstructive or enlargement procedures, with Peyronie’s disease, after injury and when documenting a real change. Home readings can prepare for an appointment in these situations, but cannot give a final diagnosis.
A snapping sound followed by rapid bruising or swelling after an injury, severe pain, or an erection that lasts four hours without subsiding requires immediate medical help, including an emergency department when needed. Do not wait for pain if an erection persists. New difficulty passing urine or a sudden marked change in shape also needs prompt assessment. EAU guideline on persistent erection; EAU guideline on genital injuries
Outside these medical questions, measuring can become a reassurance routine. Some people repeat it until a desired number appears, compare several studies and still feel better only briefly. The ruler then provides no new information and instead keeps attention fixed on the supposed flaw.
For normal size with considerable distress, the EAU recommends psychosexual or psychological assessment before considering procedures that change the body. Such counselling takes the distress seriously and helps avoid treatments that do not address the underlying body-image problem.

What a measurement cannot answer
A length does not tell you whether an erection is stable, sex will be enjoyable, someone is fertile or a partner will be satisfied. Penis shape cannot be reduced to one line either. Girth, the glans, curvature, firmness and movement work together in everyday life.
A measurement cannot establish the cause of a change either. Shorter visible length may result from a larger fat pad, a weaker erection, scarring or a different posture. Changes over time and an examination are needed to distinguish these possibilities.
If you are looking for a medical cut-off, you also need the correct reference. An adult mean is not suitable for a child, and a study using another method does not offer a fair comparison. Penis size: averages, variation and context explains these data problems in detail.
Before-and-after measurements in enlargement offers
Advertisements often use two different measurement conditions: before, from visible skin or with an incomplete erection; after, bone-pressed, with stronger stretching or from a more favourable camera angle. That creates an apparent gain without corresponding anatomical growth.
Fair documentation keeps the state, starting point, tool, posture and erection quality constant. After girth treatment, the same site on the shaft must also be used. Photographs need the same distance and angle. Without these details, before-and-after images are more marketing than evidence.
Real changes must also be assessed for durability. Swelling after injections or surgery is not a stable final result. Reliable studies report follow-up duration, participants lost to follow-up and complications, rather than only the best early measurement.
Measurement before traction or surgery
Before medical traction or a procedure, baseline readings are documented so that goals and results can be assessed realistically. With Peyronie’s disease, these include curvature, possible indentations, erection firmness and functional length. For cosmetic requests, assessment must also establish whether the original size is normal and whether marked size anxiety is present.
The EAU recommends thorough counselling before enlargement procedures. It matters whether a method changes visible flaccid length, erect length or girth. Advertising often mixes these goals together. An operation may, for instance, expose more shaft without correspondingly lengthening the erectile tissue during an erection.
Myths and facts about measuring your penis
- Myth: a flaccid measurement is enough to compare sizes.
- Fact: flaccid length varies substantially. Comparisons require a clearly defined state.
- Myth: the starting point does not matter.
- Fact: skin-based and bone-based measurements can differ considerably.
- Myth: SPL always gives the exact erect length.
- Fact: the measurements are related but can differ noticeably for an individual.
- Myth: 450 g is the prescribed pulling force.
- Fact: this figure comes from specific research protocols and is not a home or safety standard.
- Myth: a ruler alone can assess a curve.
- Fact: progression, photographs, angle, plaque, pain and function all belong in the assessment.
- Myth: measuring more often always improves reliability.
- Fact: a few standardised measurements are enough. Constant checking often just increases worry.
Conclusion
Measure erect length along the upper side from the pubic bone to the glans tip; for condoms, girth is the key measurement. Stretched penile length is a clinical tool, not a home competition with weights. With a curve, be clear whether you want to document length, angle or changes over time. A useful measurement answers a specific question. Pain, new shape changes or unusual development then need professional assessment.
Understanding the result after measuring
Continue with condom fit, reference values, micropenis and the difference between size and erection function.





